What Is the the Anion Gap?
The anion gap is a valuable laboratory measurement intended to measure the balance between positive and negatively charged electrolytes. It is not a direct measurement of a single substance; instead, it is a derived value that assists clinicians interpret an acid-base problem, especially when the body shows signs of metabolic acidosis.
In basic terms, the anion gap represents the variance between the major measured cations and anions in the blood. The most common components are sodium, chloride, and bicarbonate. Because the body works to maintain electrical neutrality, any variation in these measured values can indicate an underlying imbalance or unseen acid.
This is why the anion gap is helpful in initial screening and diagnostic evaluation. It does not reveal the whole story by itself, but it can aid identify whether an abnormal result is likely due to an acid-base disorder, an electrolyte imbalance, or another metabolic state that needs more care.
How the Anion Gap Formula Uses Sodium
An anion gap calculator typically applies a standard formula based on sodium, chloride, and bicarbonate. The most common version is:
Anion gap = sodium - (chloride + bicarbonate)
Some labs add potassium in the formula, but the sodium-based version is the most widely used one. In this calculation, sodium is the primary measured cation, while chloride and bicarbonate are the chief measured anions. The result helps estimate the amount of unmeasured ions in the blood.
Sodium matters because it is the largest contributor on the left side of the formula. Even so, sodium is usually interpreted along with the rest of the electrolyte panel rather than alone. A normal sodium value does not automatically mean the anion gap is normal, and a sodium abnormality does not always create a significant change in the calculation.
The real value of the formula is in interpretation. If sodium, chloride, and bicarbonate move in certain patterns, the calculation can reveal clues about acid-base balance, blood chemistry changes, and the presence of hidden acids such as lactate or ketones.
How Serum sodium Changes Can Alter the Anion Gap
Changes in serum sodium can affect the anion gap, but the effect depends on the broader picture in the lab values. In hyponatremia, sodium is below normal, which can decrease the calculated gap if chloride and bicarbonate do not change similarly. In hypernatremia, sodium is increased, which can increase the calculated value if the other components remain unchanged.
Still, sodium does not operate in isolation. The anion gap is a relative comparison of measured ions, so the interpretation depends on the full measurement context. A patient with low sodium may still have a high anion gap if bicarbonate drops substantially because of an underlying acid load. Likewise, a patient with high sodium may also have a normal anion gap if chloride and bicarbonate shift in a compensatory way.
That is why clinicians look at the entire lab values pattern. A sodium change can affect the calculation, but the clinical significance comes from the larger blood chemistry picture rather than from sodium alone.
Corrected Anion Gap and Albumin Compensation
Albumin is among the of the main unmeasured anions in the blood. It is also a primary binding proteins contributor in circulation, so low albumin can make the anion gap appear reduced than it really is. This is where the corrected anion gap becomes useful.
In hypoalbuminemia, the body has fewer negatively charged albumin in circulation. Because the anion gap depends on maintaining electrical neutrality, the calculated value may decrease even when there is a meaningful acid-base issue present. Correcting for albumin helps show whether the apparent normal or low result is masking a true abnormality.
Albumin adjustment matters far more than many people realize. A patient can have a seemingly normal anion gap on paper, yet still have a hidden high gap once the calculation is corrected. This is especially important in diagnostic workups where the goal is to assess the patient’s actual acid-base status rather than just accept the raw number at face value.
For that reason, the corrected anion gap is often viewed as part of a thoughtful interpretation, particularly when albumin is low or when the clinical picture does not fit the lab result. It gives a better view of whether the blood is showing a real acid-base imbalance.
Interpreting a Elevated, Normal, or Low Anion Gap
Determining whether the result is high anion gap, normal anion gap, or low anion gap https://anion-gap-chart588.almoheet-travel.com/how-renal-tubular-acidosis-affects-the-anion-gap is central to interpretation. Every pattern suggests different explanations, and the reference range provided by the lab is essential for interpretation.
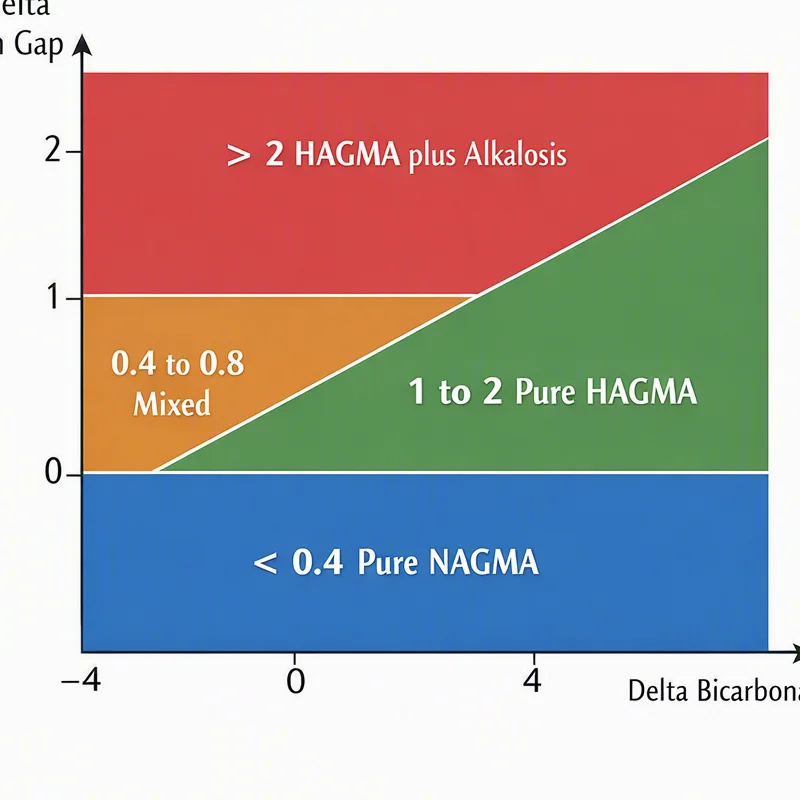
A high anion gap often suggests metabolic acidosis caused by unmeasured acids in the blood. Common causes include lactic acidosis, diabetic ketoacidosis, and renal failure. In these cases, bicarbonate is used up as the body tries to buffer excess acid, which widens the gap.
A normal anion gap does not exclude disease. It may be seen in some forms of metabolic acidosis where bicarbonate loss is offset by chloride rise, creating a balanced calculation even though the patient still has an acid-base disorder. This is why a normal result must still be interpreted in the context of symptoms and other lab findings.
A low anion gap is less common and can occur with hypoalbuminemia, lab error, or unusual changes in measured ions. It may also reflect analytical issues or shifts in blood chemistry that reduce the apparent difference between cations and anions. A low result should never be dismissed automatically; it deserves careful review of the full electrolyte panel and measurement conditions.
In all three cases, the number is a clue rather than a final answer. The diagnosis depends on the broader clinical picture, including the patient’s acid-base balance, serum levels, and other markers of metabolic state.
Common Clinical Situations Where Sodium and anion gap Rise Together
Some medical situations help clarify the relationship between sodium and anion gap easier to see. One typical example is dehydration. When body water is lost, sodium may become more concentrated, and the overall lab pattern can shift. Depending on the severity and associated electrolyte changes, the anion gap may increase, remain stable, or appear altered because of concurrent changes in chloride and bicarbonate.
Renal failure is another key situation. When the kidneys cannot remove acids effectively, unmeasured acids accumulate and the anion gap can be elevated. Sodium may also be abnormal in renal dysfunction, but the anion gap elevation is usually driven more by acid retention than by sodium alone.
Lactic acidosis is a well-known cause of high anion gap metabolic acidosis. When tissue oxygen delivery is impaired or metabolism shifts, lactate rises, bicarbonate falls, and the gap widens. Sodium may be normal, low, or high depending on fluid status, but it is not the main driver of the abnormality.
Diabetic ketoacidosis also commonly produces a high anion gap. Ketone accumulation consumes bicarbonate and creates a clear acid-base disturbance. Sodium can appear lower than expected in this setting because of osmotic effects and fluid shifts, which is why the overall interpretation must consider the electrolyte panel as a whole.
These examples show a key principle: sodium and the anion gap may shift together in some metabolic states, but the relationship is indirect. In many cases, the sodium change reflects the patient’s fluid and metabolic state, while the gap reflects the presence of unmeasured acid.
How to Use an Anion Gap Calculator Correctly
Using an anion gap calculator properly begins with the correct data. The calculator should be based on a up-to-date electrolyte panel that contains sodium, chloride, and serum bicarbonate. If the values come from different time points, the calculation may not represent the patient’s actual status.
For meaningful results, consider the specific lab panel and the units used. Small differences in measurement technique or reference method can influence interpretation. The calculator is useful for rapid screening, but the result should always be compared with the lab reference range and the patient’s clinical picture.
Proper interpretation also means looking beyond the number itself. Ask whether albumin is low, whether the patient has evidence of metabolic acidosis, and whether the acid-base pattern fits the story. A calculated value is only one piece of the evaluation, and it works best when combined with other blood chemistry markers.
In practice, the best use of the calculator is to support clinical reasoning. It helps identify whether a result needs more attention, whether a corrected anion gap should be considered, and whether the electrolyte panel suggests a hidden imbalance that requires follow-up.
Frequently Requested Inquiries About Anion Gap and Na
Does sodium actually alter the anion gap?
Sodium influences the anion gap because it is included in the formula, but it does not usually set the result by itself. The formula also depends on chloride and bicarbonate, so the broader picture matters more than sodium alone. A shift in sodium may shift the number, but interpretation still requires the full blood chemistry context.
Why is sodium included in the anion gap formula?
Sodium is included because it is the principal measured cation in the formula. The anion gap compares sodium against chloride and bicarbonate to calculate the amount of unmeasured ions. This helps check acid-base balance and spot hidden acids that may not be obvious from a basic lab panel.
Can a low sodium level cause a high anion gap?
Not usually by itself. Hyponatremia can affect the calculation, but a high anion gap is more often caused by increased unmeasured acids such as lactate or ketones. In other words, low sodium may affect interpretation, but it is not the classic cause of a high gap.
How does albumin affect the anion gap calculation?
Albumin is a major unmeasured anion, so low albumin can make the anion gap look lower than it really is. That is why the corrected anion gap is helpful in hypoalbuminemia. Adjusting for albumin improves interpretation and helps protect the meaning of the result.
When should an anion gap calculator be used with other lab values?
It should always be used with other lab values, especially sodium, chloride, bicarbonate, and albumin. The calculator is most helpful when reviewed alongside the full electrolyte panel and the patient’s symptoms. That combination gives the strongest opportunity of identifying a true acid-base disorder, lab pattern, or metabolic imbalance.