What Is a Complex Acid–Base Imbalance?
A complex acid–base disorder develops when more than one factor is altering acid-base balance at the same point. Rather than a single simple pattern, the blood reveals signs of several coexisting disturbances. This situation is significant because a patient may appear acidotic, alkalotic, or even apparently normal on paper while still having a serious root problem.
The most common pairings involve metabolic acidosis along with a additional disorder such as respiratory alkalosis. In real-world care, this means one condition is lowering bicarbonate or increasing acid load, while another is lowering carbon dioxide through hyperventilation. The outcome can be confusing unless you use a thorough assessment approach and evaluate the full clinical picture.
A combined acid–base imbalance is not just a laboratory curiosity. It often indicates a serious metabolic disturbance, ventilatory compensation that is overactive or inadequate, or an independent problem affecting the lungs and kidneys at the same moment. Because of that, result review should always include serum chemistry, blood gas analysis, and the clinical context.
What Is Elevated Anion Gap Signify?
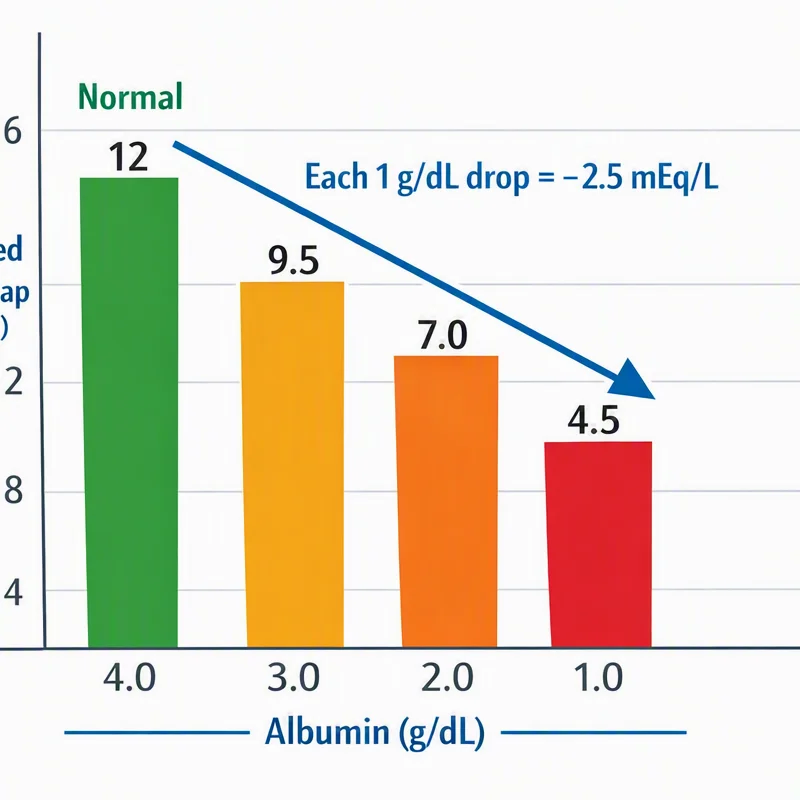
The anion gap is a calculated value used to help identify changes in electrolytes and acid-base regulation. It estimates the difference between measured cations and measured anions in the serum, and it provides a clue about the presence of unmeasured anions in the bloodstream. When the elevated anion gap is present, it usually suggests that extra acids are gathering.
An increased anion gap is most closely connected with high anion gap metabolic acidosis. In this scenario, bicarbonate is consumed while acids build up, leaving behind negatively charged byproducts that are not directly measured on a standard panel. These may come from lactic acid, ketones, toxins, or impaired renal function.
Understanding the anion gap helps focus the differential diagnosis. It does not tell you the exact cause by itself, but it clearly points to that the body is dealing with a specific type of acid loading or loss of acid excretion. That is why the anion gap is such a valuable part of laboratory interpretation.
How the Anion Gap Calculator Helps Interpretation
An Anion Gap Calculator streamlines the anion gap formula simpler to apply and reduces mistakes during rapid assessment. The calculation typically uses serum sodium, serum chloride, and serum bicarbonate. Because these values are often already available on a routine metabolic panel, the calculator turns raw serum chemistry into a more useful result.
The classic formula is: sodium minus the sum of chloride and bicarbonate. That calculated value is the anion gap. A higher number indicates the presence of extra unmeasured anions and may indicate a high anion gap metabolic acidosis. The calculator can also help you spot whether the pattern matches a single disorder or hints at a mixed acid-base disorder.
Using an Anion Gap Calculator is useful because the result alone is not enough. You still need to compare it with the blood gas, the pH, the pCO2, and the patient’s symptoms. In other words, the calculator assists clinical reasoning, but it does not replace it. The best use is as part of a broader diagnostic approach that includes compensation analysis and an underlying cause review.
Frequent Causes of Mixed Acid-Base Disorders With Increased Anion Gap
Various conditions can lead to a mixed acid-base disorder with an elevated anion gap. Some of the most common are lactic acidosis, ketoacidosis, and renal failure. Every one can produce a high anion gap metabolic acidosis, and each can also overlap with another disorder such as a respiratory alkalosis or strong respiratory compensation that is greater than expected.
Lactic acidosis develops when tissues are deprived of adequate oxygen or when cells cannot process oxygen normally. The consequence is more lactate being produced and acid accumulation. It is often seen in severe illness, reduced perfusion, seizures, or substantial metabolic stress. If the patient is also ventilating rapidly, a respiratory alkalemia may occur simultaneously and make the pH not as obviously abnormal.
Ketoacidosis occurs when ketone production rises, most often in diabetes that is not controlled, prolonged fasting, or alcohol-related metabolic stress. The ketoacids raise the anion gap and decrease bicarbonate. If the person is breathing rapidly from pain, anxiety, infection, or sepsis, the blood gas may show a second disorder on top of the acidosis.
Renal failure can also cause retention of acids that are normally excreted by the kidneys. As kidney function worsens, unaccounted acids accumulate and the serum anion gap may rise. This can happen progressively or suddenly, and it often requires thorough review to electrolyte patterns and the full serum chemistry profile.
Recognizing a Mixed Disorder from Laboratory Tests
The key to recognizing a mixed acid-base disorder is not just noticing an abnormal number. You need to analyze the arterial blood gas, including pH and pCO2, in combination with the chemistry panel. Together, these values indicate whether the body’s anion gap in end stage renal disease response is adequate or whether two separate processes are happening together.
The blood gas can show a low pH with low bicarbonate, which fits metabolic acidosis. But if the pCO2 is lower than expected, there may also be respiratory alkalosis. That is why the idea of a mixed disorder becomes important. The pH alone may not reveal the full story, especially if compensation is masking one component.
The delta gap is a second useful tool. It compares the rise in anion gap with the fall in bicarbonate. If the changes do not match expected patterns, a mixed process may be present. For example, a very high anion gap with only mild bicarbonate reduction may suggest an additional metabolic alkalosis. Likewise, an unexpectedly low pCO2 may point to superimposed respiratory alkalosis rather than simple compensation.
In practical terms, abnormal labs should raise questions like: Is the pH acidemic or alkalemic? Is the pCO2 moving in the direction you would expect? Does the anion gap fit the degree of bicarbonate loss? This approach helps identify a straightforward pattern from a more complex metabolic disturbance.
Sequential Process to Reading Results
A structured approach makes analysis much easier. To begin, review the pH to identify whether the patient is too acidic, too alkaline, or near normal. Then, determine whether the primary process appears of metabolic origin or breathing-related. Next, check the serum anion gap to see whether there is evidence of increased anion gap metabolic acidosis. This order offers a reliable foundation for laboratory interpretation.
Then, use Winter's formula to estimate the expected respiratory compensation for metabolic acidosis. If the measured pCO2 is much higher than expected, there may be an concurrent respiratory acidosis. If the pCO2 is well below than expected, respiratory alkalosis may be present. This is one of the most important steps in detecting a mixed acid-base disorder.
Finally, assess whether the observed pattern is physiologically consistent. True compensation is the body’s normal response to a primary disorder, but compensation has boundaries. When the blood gas does not fit the expected pattern, it suggests more than one process. That is often the clue that the patient has an underlying cause requiring immediate attention.
A practical rule: if the anion gap is elevated and the pCO2 does not match the expected compensatory response, think past a single diagnosis and look for a additional acid-base process.
Cases of Increased Anion Gap Mixed Disorders
One common example is a patient with sepsis who develops lactic acidosis. This infection drives reduced blood flow and lactate buildup, causing high anion gap metabolic acidosis. At the same time, the patient may hyperventilate from fever, pain, or systemic stress, producing respiratory alkalosis. The blood gas can show a pH that is not as low as expected because the two disorders partially offset each other.
A further example involves toxic alcohols. These substances can generate acids that raise the anion gap, leading to severe metabolic acidosis. If the patient is also breathing rapidly due to physiologic stress, agitation, or central nervous system effects, a mixed pattern may appear. The result is a serious diagnostic challenge that requires prompt recognition.
Salicylate poisoning is a classic mixed disorder. It often causes respiratory alkalosis early because the toxic exposure stimulates the respiratory center. Later, a high anion gap metabolic acidosis develops as acid metabolites accumulate. The combination can produce a deceptively near-normal pH, which is why blood gas analysis and serum chemistry must be reviewed together.
These examples show why laboratory interpretation matters. A patient can be severely ill even when one number seems only mildly abnormal. The anion gap formula, pH, pCO2, and clinical presentation all need to be interpreted together to identify the correct diagnosis.
When to Obtain Prompt Clinical Evaluation
Specific findings should require immediate clinical evaluation, especially when they appear alongside an elevated anion gap. Serious lab values such as a markedly reduced bicarbonate, markedly abnormal pH, or markedly elevated serum anion gap may indicate a potentially fatal metabolic disturbance. These results need prompt clinical attention rather than routine follow-up.
Clinical signs matter just as much as lab results. Altered mental status, confusion, extreme weakness, rapid breathing, chest discomfort, or inability to stay awake can all signal a critical acid-base disorder. If the patient is not protecting the airway or cannot provide a reliable history, the urgency increases.
Shock is another significant warning sign. Poor perfusion can worsen lactic acidosis and rapidly destabilize the acid-base status. In that setting, the elevated anion gap may reflect a serious underlying cause such as sepsis, toxic ingestion, or organ failure. Urgent evaluation is needed because these conditions can progress quickly.
In short, a mixed acid-base disorder with a high anion gap is not something to ignore. It can represent a serious electrolyte disorder or systemic illness that needs prompt diagnosis and treatment.
Frequently Asked Questions
What is considered an elevated anion gap?
An elevated anion gap is a above-normal result on an anion gap calculation using serum sodium, serum chloride, and serum bicarbonate. The exact cutoff can vary by laboratory because reference ranges differ, but a clearly increased value suggests excess unmeasured anions and raises concern for high anion gap metabolic acidosis. Always interpret the number with the rest of the blood gas and serum chemistry results.
How does a mixed acid-base disorder differ from a simple disorder?
A simple disorder has one primary acid-base problem with an appropriate compensatory response. A mixed acid-base disorder has two or more separate processes happening at the same time, such as metabolic acidosis plus respiratory alkalosis. The clue is often that the pH, pCO2, and bicarbonate do not fit the expected pattern for a single disorder.
Can a patient have both metabolic acidosis and respiratory alkalosis at the same time?
Absolutely. This is a textbook mixed acid-base disorder. It can happen in sepsis, salicylate poisoning, liver disease, or other disorders where the body is producing acid while also driving hyperventilation. In these cases, the pCO2 may be less than predicted for plain compensation, and the pH may appear less disturbed than the severity of illness would suggest.
What conditions most commonly cause a high anion gap?
Common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions all generate or accumulate acids that increase the anion gap. The best differential diagnosis comes from combining the anion gap with the arterial blood gas, clinical findings, and other laboratory interpretation clues.
How do you calculate and interpret the anion gap in lab results?
The anion gap formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. Anion Gap Calculator can make that process faster and minimize calculation errors. Once you have the result, evaluate it alongside the expected compensation using Winter's formula, review the pH and pCO2, and look for signs of a combined acid-base disorder. Interpretation works best when the calculated value is considered together with the patient’s symptoms and underlying cause rather than assessed in isolation.