A pattern of reduced bicarbonate combined how to calculate delta ratio step by step with a increased anion gap usually points to acid buildup in the blood, in which acids build up in the body or bicarbonate is used up while trying to buffer that acid. This is an important clue in lab interpretation because it affects how clinicians think about the likely reason for the acidosis and what testing should happen next. An Anion Gap Calculator can help arrange the numbers from a blood test, but the result always has to be interpreted in context with symptoms, the full blood chemistry panel, and other findings.
Because this pattern can reflect anything from temporary illness to a dangerous poisoning, it has important clinical significance. Understanding the relationship between the anion gap, bicarbonate, and overall acid-base status helps explain why doctors may ask for more testing even when only one part of the lab report looks abnormal.
What the Anion Gap and Bicarbonate Are Measured
The anion gap is a calculated value that helps estimate the balance between positive and negative ions in the blood. It is usually based on sodium, chloride, and bicarbonate on routine blood chemistry testing. Simply put, it can show whether there are hidden acids in the bloodstream, often described as unmeasured acids or unmeasured anions.
Bicarbonate, occasionally reported as serum bicarbonate or CO2 on a lab panel, is one of the body’s main defenses against acid. When bicarbonate is low, it often means the body is either wasting bicarbonate or consuming it while buffering acid. That is why low bicarbonate is a important clue in evaluating metabolic acidosis and broader electrolyte disturbance.
These numbers are usually part of a standard metabolic panel, which is one of the most useful pictures of the body's internal chemistry. The measurements allow doctors to read lab results, find out whether there is an acid-base problem, and determine whether more prompt action is needed.
Reasons Why Decreased Bicarbonate Levels And Increased Anion Gap Occurs
A low bicarbonate and high anion gap usually suggests the body has formed acid accumulation. In this case, acids build up at a faster rate than the body can clear them, or bicarbonate is being consumed as it neutralizes those acids. The outcome is a shift in blood pH toward acidity.
In high anion gap metabolic acidosis, the key issue is typically the existence of extra acids that are not directly measured on standard labs. These acids elevate the anion gap calculation and lower bicarbonate at the same time. This is why the pattern is so valuable: it shows that the problem is not just a chance abnormality, but a clue to a real change in the body’s chemistry.
The body may try to compensate by changing breathing patterns. More rapid or deeper breathing can reduce carbon dioxide and somewhat offset the acidity. This compensation is one reason someone with acidosis may seem to be breathing rapidly even before the cause is known.
Recognizing this pattern is central to lab interpretation. It suggests a true acid-base disorder rather than a slight incidental finding, and it should lead to a focused diagnostic evaluation when clinically appropriate.
Common Causes of High Anion Gap Metabolic Acidosis
Various significant conditions can cause high anion gap metabolic acidosis. The most common categories include lactic acid accumulation, ketone production, renal acid retention, and toxin ingestion. All of these can produce a similar lab pattern even though the actual issue is very different.
Lactic acidosis occurs when the body produces too much lactate or cannot clear it effectively. It may be seen with major infection, oxygen deprivation, shock, seizures, or additional severe stresses. As lactate increases, it becomes one of the major unmeasured acids that increases the anion gap.
Ketoacidosis is another important cause. In diabetic ketoacidosis, the body metabolizes fat quickly and produces ketones because it is unable to use glucose effectively. Ketones are acidic, so they reduce bicarbonate and raise the anion gap. Ketoacidosis can also occur with excessive alcohol use or extended fasting, though diabetic ketoacidosis is the best known form.
Renal failure can also result in this lab pattern because the kidneys normally aid in clearing acid and maintain renal function. When kidney function deteriorates, acids accumulate in the blood and bicarbonate can fall. In this setting, the anion gap may rise as retained acids build up over time.
Toxins are an especially important concern because some poisonings can lead to dangerous acidosis fast. Examples include ethylene glycol, methanol, and salicylates. These substances may cause harmful changes in blood chemistry and often require rapid treatment. If a poisoning is possible, the lab pattern should not be overlooked.
How to Understand Results With an Anion Gap Calculator
An Anion Gap Calculator is a practical tool for carrying out an anion gap calculation from standard lab values. Many calculators use sodium, chloride, and bicarbonate to estimate the gap. Some versions also allow adjustment for albumin, which can substantially affect interpretation.
The raw result is only the first step. A “normal” number may still hide an abnormal condition if albumin is low, while a slightly high number may be more meaningful when symptoms are present. That is why the tool is best used as part of a more complete blood chemistry review, not as a standalone diagnosis.
When you interpret lab results, consider the full picture:
- Sodium helps anchor the calculation. Chloride and bicarbonate help determine whether the gap is widened or narrowed. Albumin can change the expected reference range. The patient’s symptoms and clinical setting guide the next step.
An elevated anion gap with low bicarbonate strongly suggests the body is dealing with acid excess, but the calculator itself cannot determine the specific cause of acidosis. It is a supportive and interpretation aid, not a final answer.
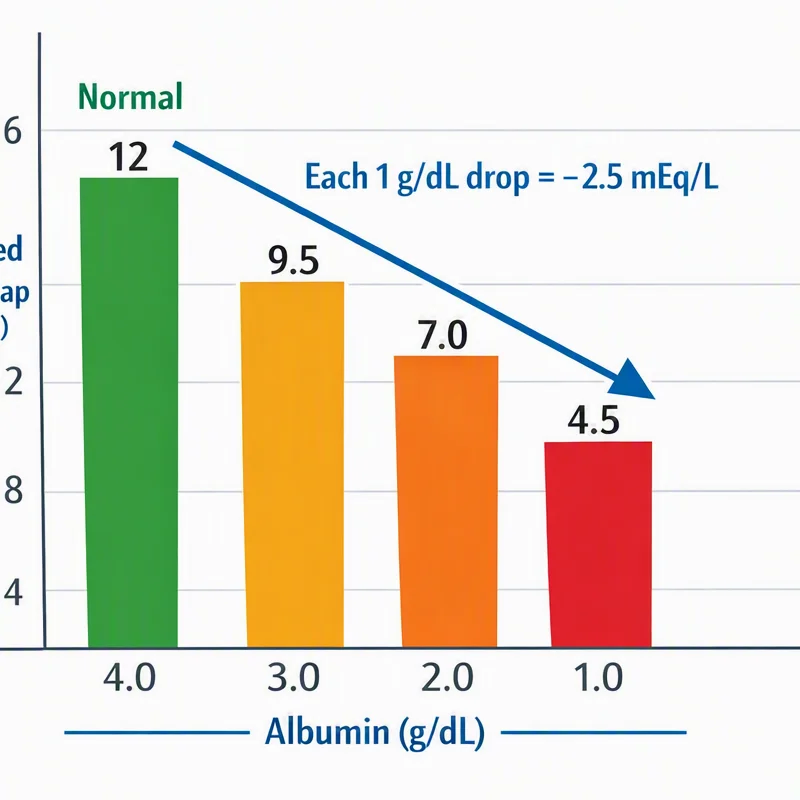
Correcting the Anion Gap for Albumin
Albumin correction is important because albumin is a major unmeasured anion in blood. When albumin is low, the measured anion gap can appear falsely normal or only mildly elevated even when a serious acid-base disorder is present. This is especially important in hospitalized patients, people with inflammation, malnutrition, liver disease, or other causes of hypoalbuminemia.
Without albumin correction, the reference range can be misleading. A clinician may estimate the corrected anion gap by considering how much albumin is below normal. That adjustment makes the result more accurate and boosts the chance of detecting true high anion gap states.
When an Anion Gap Calculator incorporates albumin, it can more completely reflect the real acid burden. If not, the result should be read with caution, especially when there is signs of decreased albumin or severe illness.
Signs That Can Occur With elevated anion gap and low bicarbonate
Signs can change depending on the root cause, how intense the acidosis is, and how rapidly it appeared. Certain people have noticeable symptoms of acidosis, while others may only show abnormal lab values initially.
Common indicators include breathlessness, tiredness, confusion, and fast breathing. Rapid breathing may be the body’s way of adjusting for the acidosis by reducing carbon dioxide. In more serious cases, a person may appear weak, very sleepy, or unable to think clearly.
The overall symptom profile can also give clues about the cause. For example, nausea, vomiting, abdominal pain, and excessive thirst may be consistent with ketoacidosis, while weakness and confusion may suggest kidney-related acid retention or toxin exposure. Because the same lab pattern can come from very different problems, symptoms always matter in the overall evaluation.
When Low Bicarbonate Is Not a High Anion Gap Problem
Low bicarbonate does not necessarily mean high anion gap metabolic acidosis. In some situations, the cause is a normal anion gap acidosis, also called hyperchloremic acidosis. In that setting, bicarbonate is low, but chloride rises to counterbalance the charge, so the anion gap remains within the expected range.
Diarrhea is a typical cause because the body loses bicarbonate through the gastrointestinal tract. Another major cause is renal tubular acidosis, where the kidneys fail to handle acid properly even if overall renal function is not severely reduced.
Chloride plays an especially important role here. When chloride increases as bicarbonate falls, the anion gap may stay normal. That is why the distinction between high and normal anion gap acidosis is so useful in medical attention and follow-up testing. The pattern changes the differential diagnosis and directs the clinician toward different possibilities.
Exams Physicians Order to Identify the Cause
If the lab pattern suggests acidosis, clinicians often request additional studies to determine the exact source. The aim is to move from pattern recognition to a clear diagnosis.
An arterial blood gas is one of the most important follow-up tests because it measures blood pH, carbon dioxide, and oxygen status directly. This helps confirm whether the issue is truly an acid-base disorder and how severe it is.
Common common tests include lactate, which helps detect lactic acidosis, and ketones, which are useful when ketoacidosis or diabetic ketoacidosis is suspected. A creatinine level helps assess kidney function and can point toward kidney failure or reduced clearance of acids. Depending on the situation, clinicians may also check toxicology studies if toxins are possible.
For this reason an abnormal anion gap should not be treated as a standalone result. The combination of symptoms, history, and targeted tests creates the full diagnostic evaluation. An Anion Gap Calculator can help identify the pattern, but the next step is finding the reason behind it.
How to Respond If Your Lab Results Show This Pattern
If your labs show low bicarbonate with a high anion gap, the right next step depends on symptoms and overall health. In many cases, this pattern needs prompt medical evaluation because the underlying cause can be serious. If symptoms are severe or rapidly worsening, urgent care or emergency evaluation may be appropriate.
Don’t assume the finding is harmless. A high anion gap can reflect lactic acidosis, ketoacidosis, kidney failure, or exposure to dangerous substances such as ethylene glycol, methanol, or salicylates. Even if you feel relatively well, the lab pattern deserves attention because some causes progress quickly.
Repeating the test is sometimes helpful if there is worry for a lab error or if the result does not align with the clinical picture. That said, repeating the test should not delay evaluation when the patient is ill. The main goal is to identify the source and treat it promptly.
If the pattern appears on a blood chemistry panel, a clinician may review the full blood chemistry, check albumin for possible correction for albumin, assess renal function, and decide whether an ABG, lactate, or ketones are needed. In other words, the lab result is the start of the workup, not the end.
When used appropriately, an Anion Gap Calculator helps with faster recognition of dangerous acid-base disorders. It helps clinicians and patients alike understand lab results, understand the possibility of acid-base imbalance, and decide when more immediate action is necessary.
FAQ
What does a low bicarbonate with high anion gap mean?
It usually means there is acidotic imbalance with acid accumulation in the blood. The pattern suggests the body has extra acids or is retaining acids, which lowers blood bicarbonate and raises the anion gap.
What are the most common causes of high anion gap metabolic acidosis?
The most common causes include lactic acid buildup, ketoacidosis, diabetic ketoacidosis, renal failure, and toxins such as ethylene glycol, methanol, and salicylates.
Can dehydration cause a high anion gap and low bicarbonate?
Dehydration by itself does not usually cause this pattern, but severe dehydration can contribute indirectly by reducing circulation, worsening lactate buildup, or triggering ketoacidosis. The real reason for acidosis still needs evaluation.
How do you calculate the anion gap from lab results?
The basic anion gap calculation relies on sodium minus the sum of chloride along with bicarbonate. Some formulas may include potassium, but many providers use the basic version. An Anion Gap Calculator can calculate it fast and may also help with albumin correction.
When should I seek urgent medical care for these lab findings?
Get urgent medical attention if the lab pattern comes with shortness of breath, confusion, rapid breathing, marked weakness, vomiting, or possible poisoning. This can indicate severe metabolic acidosis and need prompt evaluation.