What an Anion Gap Measures
An anion gap is a calculated value that helps healthcare providers assess the balance between primary electrolytes in the blood. It is based mainly on sodium, chloride, and bicarbonate, which are routinely reported on regular chemistry panels. Even though the number itself is calculated, it can indicate important clues about an acid-base imbalance or a broader metabolic disorder.
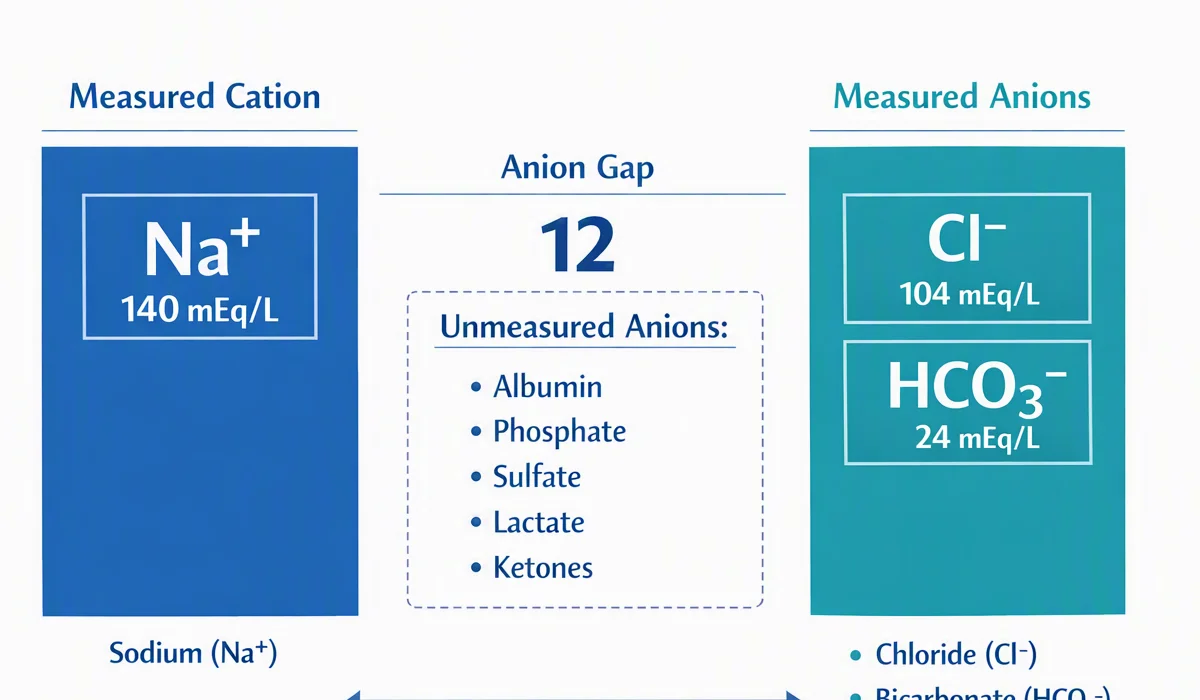
The core concept is straightforward: blood contains positively charged particles and negatively charged particles, and these should remain in a fairly steady balance. The anion gap calculator estimates the gap between measured cations and measured anions. A change in that difference can suggest the presence of unmeasured anions in the bloodstream.
Clinicians use this result as part of clinical assessment and lab interpretation, especially when they need to determine whether a patient’s acid-base balance is moving in a harmful direction. The anion gap is not a standalone diagnosis, but it is a valuable diagnostic tool that helps interpret other serum electrolytes and blood chemistry results.
How an Anion Gap Calculator Is Used
An anion gap calculator is employed to rapidly calculate anion gap from values already provided in a serum chemistry panel or a basic metabolic panel. These lab panels are common forms of blood test reporting, and they give a practical snapshot of key blood chemistry markers. The calculator uses the reported numbers and returns an anion gap result that can be reviewed during medical interpretation.
In practice, the calculator is often applied during a physician evaluation when a patient has unexplained symptoms, abnormal labs, or concern for an acid-base problem. It helps organize the next steps in a metabolic acidosis workup by showing whether the issue may suggest excess acids, a loss of bicarbonate, or another shift in serum electrolytes.
Some calculators also help users grasp normal values by comparing the result with a reference range. This can be helpful for anyone trying to make sense of a lab panel, although final test interpretation should always be done in context. The number is most meaningful when combined with symptoms, other lab data, and the overall clinical picture.
Why Clinicians Prescribe an Anion Gap Test
Healthcare providers order an anion gap test to assess metabolic acidosis and other forms of acid-base balance disruption. A rising or lowering anion gap can indicate an underlying problem that is not easily seen from symptoms alone. Because the result reflects how measured ions relate to each other, it can help spot an electrolyte imbalance that may otherwise be missed.
That is especially useful when a person appears ill, has altered breathing patterns, or has lab findings that suggest a broader metabolic issue. The anion gap is often one piece of a larger workup that may include repeat blood testing, kidney markers, glucose levels, and a blood gas. Together, these findings support more accurate diagnosis and treatment planning.
Another reason the test is ordered is to help evaluate kidney function. The kidneys help regulate acid and electrolyte levels, so reduced function can change the balance of acids and bases in the blood. When kidney performance declines, the anion gap may go up as acids accumulate or may help confirm that something more than simple dehydration is happening.
How High and Reduced Anion Gap Findings Can Mean
A high anion gap typically suggests there are additional acids in the blood or that unmeasured substances are affecting the calculation. This is often a sign of a serious acid-base problem and can help clinicians identify conditions such as lactic acidosis, diabetic ketoacidosis, or other illnesses that produce acid rapidly. A high result does not name the cause by itself, but it assists in narrowing the differential diagnosis.
A low anion gap is less common, but it can be just as significant to notice. It may occur when albumin is low, when lab values are affected by procedural or measurement issues, or when other substances are influencing the balance of charges in the blood. In some cases, a low result is a clue to a hidden condition; in other cases, it is a temporary finding that should be rechecked.
Both results need careful context. A single number should not be treated as a diagnosis. Instead, it is one data point used in lab interpretation, especially when the clinician is trying to understand an unexplained anion gap result in relation to symptoms, other chemistry values, and the patient’s overall condition.
Common Causes of a Raised Anion Gap
One common cause of an elevated anion gap is diabetic ketoacidosis, a serious complication of diabetes in which acidic ketones accumulate in the blood. A further cause is exposure to toxins, which can add or trigger acids that shift the expected electrolyte relationship. Such causes are especially important because they may require urgent evaluation and treatment.
Lactic acidosis is a further major cause of an abnormal result. It can develop when tissues do not get enough oxygen or when severe illness changes how the body produces and clears lactate. This condition is often seen with infection, shock, or other critical illnesses, and it is a key reason clinicians monitor the anion gap in acute care.
Albumin also matters because it is a major negatively charged protein in the blood. When albumin is low, the anion gap may look smaller than expected even if an acid-base problem is present. In addition, kidney disease and renal failure can cause abnormal retention of acids, shifting the result above normal. GOLD MARK breakdown Because of that, clinicians frequently interpret the anion gap alongside kidney labs and the patient’s history.
How to Understand the Result with Additional Labs
Interpreting the finding correctly begins with the anion gap formula, which uses sodium, chloride, and bicarbonate to determine the gap between measured cations and anions. But the formula alone is not sufficient. anion gap in chronic kidney disease Clinicians often order a blood gas to see whether the patient is too acidic or alkalotic and to understand how well breathing and metabolism are compensating.
Potassium may also be considered, even though it is not always part of the standard formula. It can help define the broader electrolyte pattern and may influence the full clinical picture. In some situations, the lab panel includes enough information to point to an answer quickly; in others, the pattern is subtle and requires more workup.
Albumin correction is especially important when albumin is abnormal. A corrected anion gap can provide a more accurate estimate of whether the true gap is elevated. This matters because low albumin can hide an otherwise meaningful abnormality. By applying albumin correction, clinicians improve the quality of medical interpretation and lower the chance of missing a serious disorder.
In short, the anion gap should be read as part of a full lab panel, not as a stand-alone finding. The best interpretation comes from combining the result with symptoms, history, and other data from the serum chemistry panel or basic metabolic panel.
When an Anion Gap Result Calls for Medical Review
An abnormal anion gap calls for clinical attention when it appears with concerning symptoms or when the overall clinical picture suggests a potentially serious metabolic problem. Symptoms such as confusion, rapid breathing, extreme weakness, nausea and vomiting, or critical illness can indicate that the body is struggling to maintain normal acid-base balance. In these cases, the lab result may be an initial warning sign rather than a simple abnormality on paper.
Emergency care may be needed if the abnormal result is paired with signs of poor perfusion, severe dehydration, altered mental status, or suspected poisoning. Conditions like sepsis can also drive major changes in the anion gap, especially when lactic acidosis develops. In such situations, the number helps support rapid diagnosis and treatment, but it should never delay urgent clinical action.
Dehydration can also affect the lab picture, sometimes making abnormalities look more pronounced. Even if a result turns out to be temporary, it is worth reviewing when the patient has symptoms or abnormal findings that do not fit a simple explanation. A clinician may repeat testing, order a blood gas, or evaluate for kidney involvement and other causes of acid-base disturbance.
FAQs On Anion Gap Calculators
What information does an anion gap calculator reveal
An anion gap calculator gives you the estimated difference between key measured electrolytes in the blood, primarily sodium, chloride, and bicarbonate. It helps show whether there may be extra acids or other unmeasured substances affecting the blood’s acid-base balance. Clinicians use it as a diagnostic tool to support lab interpretation and guide next steps.
What’s a normal anion gap range?
The normal range can vary a bit depending on the lab and the formula used, so the reference range on the report matters. Because of that variation, it is best to use the specific range shown with the lab values rather than assuming one universal number. The most important question is whether the result is within that lab’s normal values.
Does a high anion gap always mean a serious problem?
Not always, but it can suggest a significant issue that deserves prompt evaluation. A high anion gap is often seen with metabolic acidosis, lactic acidosis, diabetic ketoacidosis, kidney disease, or toxins. The seriousness depends on the full clinical context, including symptoms, the blood gas, and other abnormal labs.
Can a low anion gap be harmless?
Yes, sometimes a low anion gap is temporary or related to a non-dangerous lab variation. However, it can also occur when albumin is low or when another condition is affecting the calculation. If the result is unexpectedly low, clinicians may repeat the test and review the full lab panel to make sure nothing important is being missed.
Why is albumin important when interpreting the anion gap?
Albumin is important because it carries a negative charge and has a major effect on the anion gap result. When albumin is low, the gap may appear lower than it really is, which is why albumin correction can be useful. A corrected anion gap gives a more accurate view of whether there is a true acid-base disorder or an unmeasured anion problem.