What an Anion Gap Calculator Measures
An anion gap is a computed result that helps evaluate electrolytes and identify patterns of metabolic acidosis. An Anion Gap Calculator uses routine laboratory values to determine the difference between standard measured ions and the unmeasured acid components in the blood. This makes it a practical screening tool for spotting an acid-base disorder that may not be obvious from symptoms alone.
In a typical serum chemistry panel, the calculation looks at the ratio between positively charged and negatively charged particles. The result mirrors the body’s acid-base balance and can point toward an electrolyte imbalance, a metabolic derangement, or another cause of acid buildup. Because the anion gap is influenced by measured ions as well as unmeasured anions, it is often used as part of broader diagnostic support rather than as a stand-alone answer.
Clinically, the anion gap is most helpful when a patient’s laboratory values suggest acidosis. A widened gap can indicate accumulation of acids such as lactate or ketones, while a normal result can suggest a different type of problem. The calculator gives a fast way to translate raw numbers into meaningful clinical interpretation, especially when paired with the patient’s symptoms and other laboratory values.
The anion gap is not a diagnosis by itself; it is a clue that helps narrow the differential diagnosis.How Venous Blood Gas Can Be Used
A venous blood gas is usually enough for assessing many acid-base concerns because it provides useful information about pH, bicarbonate, and pCO2. Though an arterial blood gas remains important in some settings, venous sampling is commonly used when the goal is to measure metabolic status and estimate the presence of metabolic acidosis.
For anion gap calculation, the key inputs are usually part of a chemistry panel rather than the gas sample itself. Nevertheless, venous blood gas results supply important physiologic context. If the pH is low and bicarbonate is reduced, the anion gap can help determine whether the cause is a high anion gap metabolic acidosis or a process with a normal gap. The pCO2 is also useful because it helps show whether respiratory compensation is occurring appropriately.
Venous blood gas analysis is particularly useful because it is rapid, low in invasiveness, and often easier to obtain than arterial sampling. In practice, the calculator works best when venous gas data are interpreted alongside the serum chemistry panel. Together, these results provide a better picture of the patient’s acid-base disorder and overall buffer system status.
Formula and Calculator Inputs for Anion Gap
The most widely used calculation formula for the anion gap is based on sodium, chloride, and bicarbonate:
Anion gap = sodium - (chloride + bicarbonate)
Some tools also add potassium in the equation:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
Both forms estimate the difference between measured cations and measured anions. The version without potassium is used more often because potassium is a smaller contributor to the gap in many routine clinical settings. The calculator’s goal is to identify an anion deficit or increase that may reflect unmeasured acids in the circulation.
For the most accurate results, use values from the same time period and the same lab system when possible. The inputs should come from a reliable electrolyte panel and should match the values used in the patient’s blood gas analysis. A small mismatch between panels can affect result interpretation, especially when the anion gap is only mildly abnormal.
The usual inputs include:
- Sodium Chloride Bicarbonate Potassium, if the formula includes it
Because it is based on routine laboratory values, the calculator is a convenient tool for quick bedside reasoning and broader clinical review.
How to Interpret a Normal, High, or Low Anion Gap
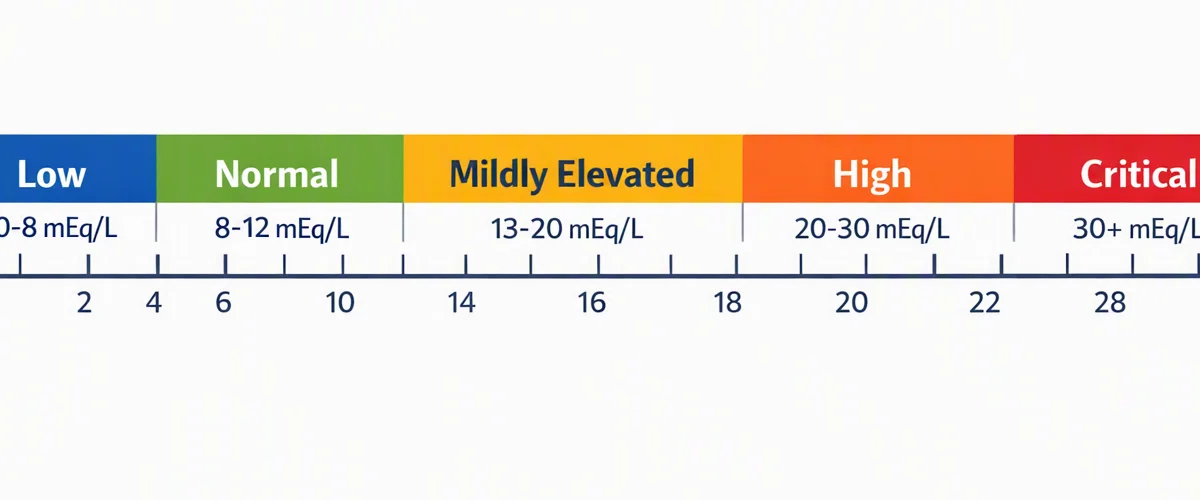
A normal anion gap indicates that the drop in bicarbonate is being matched by an increase in chloride. This pattern is frequently called normal-gap metabolic acidosis, also known as hyperchloremic acidosis. In this situation, the problem is usually associated to bicarbonate loss or reduced acid handling rather than a buildup of unmeasured acids.
A elevated anion gap metabolic acidosis means that unmeasured acids are building up. This is the pattern clinicians look for when evaluating metabolic acidosis from causes such as lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or uremia. The larger the gap, the more strongly it suggests the presence of additional unmeasured anions.
A reduced anion gap is rarer but still important. It can be caused by decreased albumin, laboratory variation, or unusual conditions that alter the relationship between measured ions and unmeasured anions. A extremely low result should not be dismissed, especially if the clinical picture suggests another issue.
Understanding the result always requires the full clinical picture. A single number cannot explain the full story about an acid-base disorder. The best use of the calculator is as a decision aid that improves result interpretation when interpreted alongside with pH, pCO2, bicarbonate, and symptoms.
Serum albumin Correction and Practical Caveats
Albumin serves as one of the key unmeasured anions in blood, so low albumin can make the anion gap appear incorrectly normal. That is why hypoalbuminemia plays such a big role when using an Anion Gap Calculator. If albumin is reduced, the measured anion gap may underestimate the presence of an underlying acid load.
An albumin-corrected anion gap adjusts the raw result using a correction factor based on the albumin level. This can help reveal hidden gaps that might otherwise be missed. The correction is particularly useful when evaluating suspected lactic acidosis, ketoacidosis, or mixed disorders in patients with low albumin.
For example, a patient with low albumin may have a mildly abnormal anion gap even though the true burden of unmeasured anions is significant. Correcting for albumin can enhance clinical judgment and clarify the differential diagnosis. However, the corrected result still must be interpreted in the context of the full presentation.
Key caveats include:
- Albumin can alter the expected reference range for the anion gap. Correction enhances sensitivity for hidden metabolic derangement. The corrected number does not remove the need for clinical interpretation.
Typical Causes of Elevated Anion Gap
A raised anion gap usually means there are extra acids in the system. The most common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and uremia. Each cause boosts the concentration of unmeasured anions and pushes the balance away from normal acid-base balance.
Lactic acidosis occurs when lactate rises, often due to tissue hypoperfusion, severe illness, or impaired oxygen delivery. Ketoacidosis appears when ketone bodies accumulate, which can happen in diabetes, starvation, or alcohol-related metabolic states. Both result in a high anion gap metabolic acidosis.
Renal failure leads to retention of acids that the kidneys normally eliminate, while uremia reflects the buildup of uremic acids and other retained solutes. Toxic alcohols such as methanol or ethylene glycol can also create a marked gap by generating organic acids after metabolism.
Because these conditions can look similar on the calculator, the anion gap should be viewed as a screening tool, not a final answer. The next step is to match the lab pattern to the patient’s symptoms, history, and other laboratory results.
Constraints With Venous Blood Gas Values
While a venous blood gas is helpful, it does not fully substitute for an arterial blood gas in every situation. Venous pH and pCO2 are useful for trending and for overall acid-base assessment, but they may not reflect oxygenation status the way an arterial sample does. Thus, the choice of test should depend on the clinical question.
There is a risk of sampling error. When the blood draw is delayed, contaminated, or not matched with the chemistry panel, the calculator result may be misleading. Minor discrepancies between specimens can matter when the anion gap is near the upper end of the reference range.
Laboratory variation is an additional important limitation. Different analyzers can produce slightly different sodium, chloride, or bicarbonate values, which changes the final result. This is why the same patient may have modestly different anion gap values across institutions or even between testing platforms.
In the end, the anion gap should never be read outside its clinical context. A normal result does not exclude all metabolic problems, and a high result does not specify the exact cause. It is one piece of a larger diagnostic picture, supported by blood gas analysis, examination, and targeted testing.
Step-by-Step Sample Calculation
This is a basic sample calculation using a common chemistry panel and venous blood gas data. Suppose the electrolyte results shows:
- Sodium: 140 Chloride: 100 Bicarbonate: 16
With the usual formula:
Anion gap = 140 - (100 + 16) = 24
If potassium also be added albumin corrected AG equation and the level is 4.0, the formula becomes:
Anion gap = (140 + 4) - (100 + 16) = 28
Now add the venous blood gas values. If the venous pH is low and pCO2 is also reduced, that anion gap in chronic kidney disease supports a primary metabolic process with respiratory compensation. A bicarbonate of 16 and an elevated anion gap together suggest high anion gap metabolic acidosis.
Next, consider albumin. Should albumin is low, the raw number may underestimate the true gap. After applying albumin adjustment, the result may move even higher, increasing suspicion for hidden acids such as lactate or ketones. This is how the calculator supports result interpretation rather than replacing it.
Normal range matters as well. If the lab’s expected range is 8 to 12, then a result of 24 is clearly elevated. If the value is only slightly above the range, the full picture becomes even more important, including symptoms, medications, and the rest of the laboratory profile.
Common Questions
How do you calculate an anion gap from venous blood gas results?
The anion gap is usually calculated from the electrolyte panel, not directly from the venous blood gas. You use sodium, chloride, and bicarbonate in the formula, then interpret the result alongside venous pH and pCO2. The Anion Gap Calculator helps merge these values into a clearer picture of acid-base status.
Can venous blood gas replace arterial blood gas for anion gap interpretation?
In many situations, yes. A venous gas gives helpful information about pH, bicarbonate, and pCO2 for evaluating metabolic problems. However, an ABG may still be needed when oxygenation or precise respiratory assessment is important.
When should the anion gap be corrected for albumin?
Adjust the value when albumin is low or suspected to be low, especially if the raw anion gap seems normal despite signs of acidosis. Hypoalbuminemia can conceal a true elevation, so the albumin-corrected anion gap gives better diagnostic support.
What does a high anion gap mean on a venous blood gas?
A elevated result usually suggests high anion gap metabolic acidosis, which can be caused by lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or uremia. The finding should be considered with the venous pH, pCO2, and the broader clinical picture.
What are the limitations of an anion gap calculator?
An anion gap calculator relies on accurate laboratory values, so sampling error and laboratory variation can alter the result. It also does not identify the exact cause of the abnormality. It works best as a screening tool within a broader clinical interpretation of the patient’s acid-base disorder.