What does the anion gap represent?
The anion gap is a calculated value used to help assess acid-base balance from a usual electrolyte panel or serum chemistry. It compares major observed cations and anions, typically using sodium, chloride, and bicarbonate. Because not all charged particles are directly measured, the anion gap approximates the amount of unmeasured anions in the blood.
In its standard form, the calculation is:
Anion gap = sodium - (chloride + bicarbonate)
Some formulas include potassium, but many clinicians use the simpler version without it because potassium contributes less to the final value. The key idea is that a rising gap can suggest a metabolic derangement caused by acids or other unmeasured substances.
Understanding the anion gap normal range matters because a value that looks “normal” may still be misleading if albumin is low or if there are mixed disorders. That is why interpretation should always happen in clinical context, not in isolation alone.
Why septic illness alters the anion gap
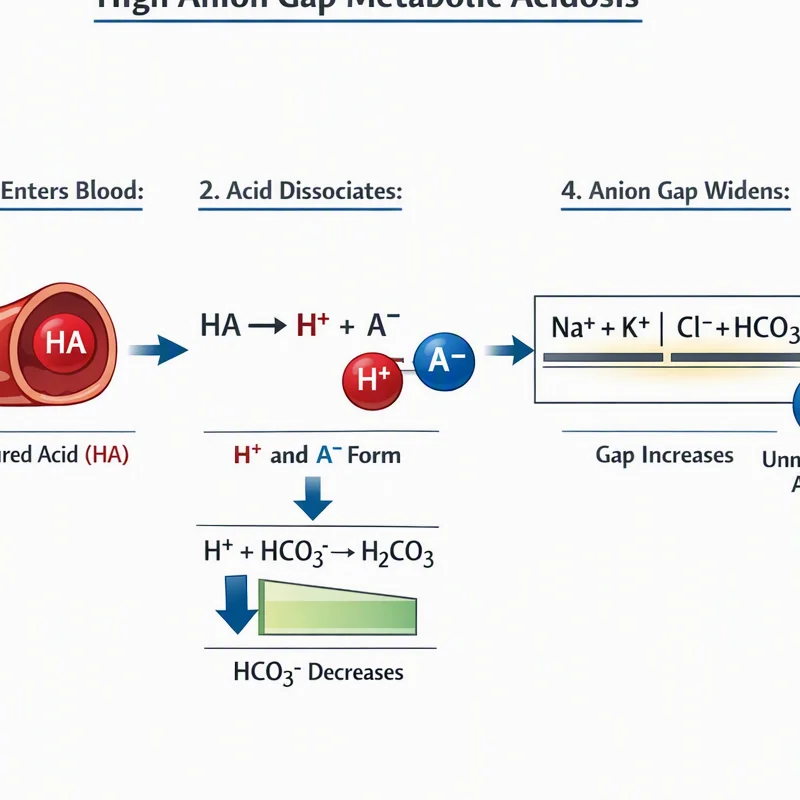
Sepsis can alter the anion gap because it often causes metabolic acidosis, especially when oxygen delivery and utilization are impaired. In a shock state, tissues may not receive enough oxygen, leading to tissue hypoperfusion and increased anaerobic metabolism. This can boost acid production, especially lactic acidosis, which raises the gap.
When cells generate excess lactate, hydrogen ions accumulate and bicarbonate is consumed buffering the acid. The result is often a lower bicarbonate level and an anion gap elevation. In sepsis, this pattern is a helpful diagnostic clue because it may reflect occult hypoperfusion even before blood pressure becomes severely abnormal.
Sepsis also produces a broader inflammatory and metabolic response that can contribute to organ dysfunction. Kidney involvement, altered perfusion, and changes in acid handling may all influence the gap. In other words, the anion gap is not just about lactate; it is a window into the biochemical effects of critical illness.
How to determine and correct the anion gap
You can calculate the anion gap manually, but an anion gap calculator is often valuable for fast analysis and for limiting arithmetic errors. The calculator typically uses sodium, chloride, and bicarbonate, and some tools enable you to use potassium. Even so, the number should always be evaluated alongside the patient’s overall acid–base picture.
One of the most important adjustments is the corrected anion gap, also called the albumin-corrected gap. Because albumin is a major unmeasured anion, low albumin can make the gap appear incorrectly low or “normal.” In sepsis, hypoalbuminemia is often seen, so the uncorrected value may underestimate the true burden of acids.
A practical approach is to:
- Review the sodium, chloride, and bicarbonate values from the chemistry panel. Determine the anion gap using a consistent formula. Review albumin and consider an albumin-corrected gap if it is low. Compare the result with the blood gas and serum lactate.
Correction does not override clinical judgment. It simply improves accuracy when assessing whether the patient has hidden acid accumulation. In septic patients, this step can prevent a missed diagnosis of ongoing acid generation.
High anion gap versus expected-range anion gap in sepsis
In sepsis, a high anion gap metabolic acidosis often points to buildup of organic acids, especially lactate. This is the classic pattern when tissue oxygen delivery is impaired. However, sepsis can also present with normal anion gap metabolic acidosis, particularly when bicarbonate is lost or when chloride https://anion-gap-reference112.timeforchangecounselling.com/in-what-way-sodium-chloride-and-bicarbonate-levels-influence-the-anion-gap rises relative to bicarbonate after large-volume fluid resuscitation.
This difference matters because a normal gap does not rule out significant illness. A patient may still have acidemia, elevated lactate, or impaired perfusion even if the calculated gap stays within the expected range. Mixed disorders are common in critical illness, so a “normal” result may mask concurrent problems.
Lactate is often the leading driver of a high gap in sepsis, but it is not the only one. If the patient has kidney injury, acids can accumulate because renal clearance is reduced. This can further increase the gap or complicate the pattern seen on the blood gas.
It is helpful to think the anion gap as a clue to the type of acidosis:
- High anion gap metabolic acidosis suggests unmeasured acids such as lactate or ketones. Normal anion gap metabolic acidosis suggests bicarbonate loss, chloride gain, or mixed physiology.
In sepsis, both patterns may occur over time as the patient’s perfusion, kidney function, and treatment response evolve.
Main causes for elevated anion gap among septic patients with sepsis
The most common cause of an increased gap in sepsis is lactate from an excess of lactic acid. This can be caused by reduced tissue blood flow, microcirculatory dysfunction, or impaired oxygen utilization. But an elevated anion gap should not be assumed to be lactate alone.
Other key causes include:
- Ketoacidosis, particularly if the patient has diabetes, poor intake, or severe stress physiology. Kidney failure, which reduces acid excretion and allows unmeasured anions to accumulate. Toxic alcohol ingestion, such as methanol or ethylene glycol, which are less common but high-risk and should be considered when the story does not fit sepsis alone.
These other causes matter because sepsis can coexist with other metabolic problems. A patient may have infection plus ketoacidosis, or sepsis plus renal failure. It should therefore prompt a broader differential rather than a single-track conclusion.
If the anion gap is rising and lactate is not very high, clinicians should consider whether another process is contributing. That is one reason serial assessment is more useful than a single isolated number.
Clinical interpretation: what this value can and cannot show
The anion gap is best used as a diagnostic clue, not a standalone diagnosis. It can suggest the presence of an acid-base disorder, but it does not identify the exact cause by itself. In sepsis, this is especially important because multiple processes can overlap at once.
A high gap may indicate accumulating unmeasured acids, but the number alone cannot tell you whether the cause is lactate, ketoacidosis, renal failure, or a toxin. Likewise, a normal gap does not exclude clinically important illness. That is why the anion gap must be paired with a blood gas analysis, lactate level, kidney function, and the overall exam.
One useful way to read the number is to ask three questions:
- Is there low pH on the blood gas? Is the anion gap elevated after considering albumin? Does the pattern fit the patient’s clinical context and circulatory status?
If the answer is yes to all three, the concern for clinically significant acid accumulation is higher. If there is a mismatch, think anion gap in chronic kidney disease about mixed acid-base disease, laboratory timing issues, or a non-lactate cause of metabolic derangement.
In short, the number does not replace bedside assessment. It supports or reduces a hypothesis about what is happening physiologically.
When to repeat labs and assess severity
For patients with sepsis, serial testing is often more useful than a single snapshot. Repeated lactate levels help determine whether the patient is reducing lactate or continuing to produce it. Likewise, repeating the electrolyte panel can show whether the anion gap is decreasing, stable, or worsening.
Providers also assess base deficit on the blood gas as another marker of metabolic burden. A worsening base deficit may suggest ongoing acidosis even if the gap has not yet altered substantially. Together, these values can help with assessing severity and treatment response.
Repeat labs are especially useful when:
- The initial lactate is elevated and you want to follow clearance of lactate. There is suspicion for persistent blood flow problems. The patient has worsening organ function or suspected kidney failure. The initial anion gap and blood gas fail to match the clinical picture.
Trending the numbers can reveal better perfusion after resuscitation or a subtle worsening that requires escalation. In critical illness, the trajectory often carries more weight than the single value.
Common questions about anion gap during sepsis
What can anion gap tell you in sepsis?
In sepsis, the anion gap helps detect whether there is a metabolic acidosis with unmeasured acids in blood. An elevated gap can suggest lactic acidosis due to tissue hypoperfusion, but it may also reflect ketoacidosis, renal failure, or toxic alcohol exposure. It is a useful clue, not an independent diagnosis.
Can sepsis cause a normal anion gap?
Yes, it can. Sepsis can cause a normal anion gap metabolic acidosis, especially when bicarbonate is lost or chloride rises during fluid treatment. A normal gap does not rule out serious illness, elevated lactate, or poor perfusion. Mixed acid-base disorders are common in sepsis.
Why do you correct the anion gap for albumin?
Albumin is a major unmeasured anion, so low albumin can make the measured anion gap look deceptively normal. Correcting for albumin gives a more accurate picture of the true acid burden. This is especially important in critical illness, where hypoalbuminemia is common.
Does a high anion gap necessarily mean lactic acidosis in sepsis?
No. Lactic acidosis is common, but a high anion gap can also come from ketoacidosis, renal failure, or toxic alcohols. The anion gap should always be interpreted with the blood gas, serum lactate, albumin, and the rest of the clinical context.
When is it best for an anion gap be repeated in a septic patient?
Repeat it when you are monitoring response to treatment, especially if lactate is elevated, perfusion is uncertain, or the patient’s condition is changing. Trending the anion gap with serial lactate, electrolytes, and base deficit helps show whether the metabolic derangement is improving or worsening.