What the anion gap measures
The anion gap is a practical way to interpret electrolytes on a blood test and search for hidden acid-base disturbances. It is usually computed from sodium, chloride, and bicarbonate, which is often reported as carbon dioxide on a chemistry panel. Because the body must maintain acid-base balance, changes in these laboratory values can reveal whether there are excess acids or unmeasured substances in the blood.
The core concept is simple: the blood contains measured positive and negative ions, but not every charged particle is directly reported. The gap reflects the difference between major cations and anions, giving a clue about anion concentration and the presence of unmeasured anions. In everyday clinical interpretation, this becomes a diagnostic clue for conditions such as metabolic acidosis or other metabolic disorder patterns.
A commonly used calculation formula is:
Anion gap = sodium - chloride - bicarbonate
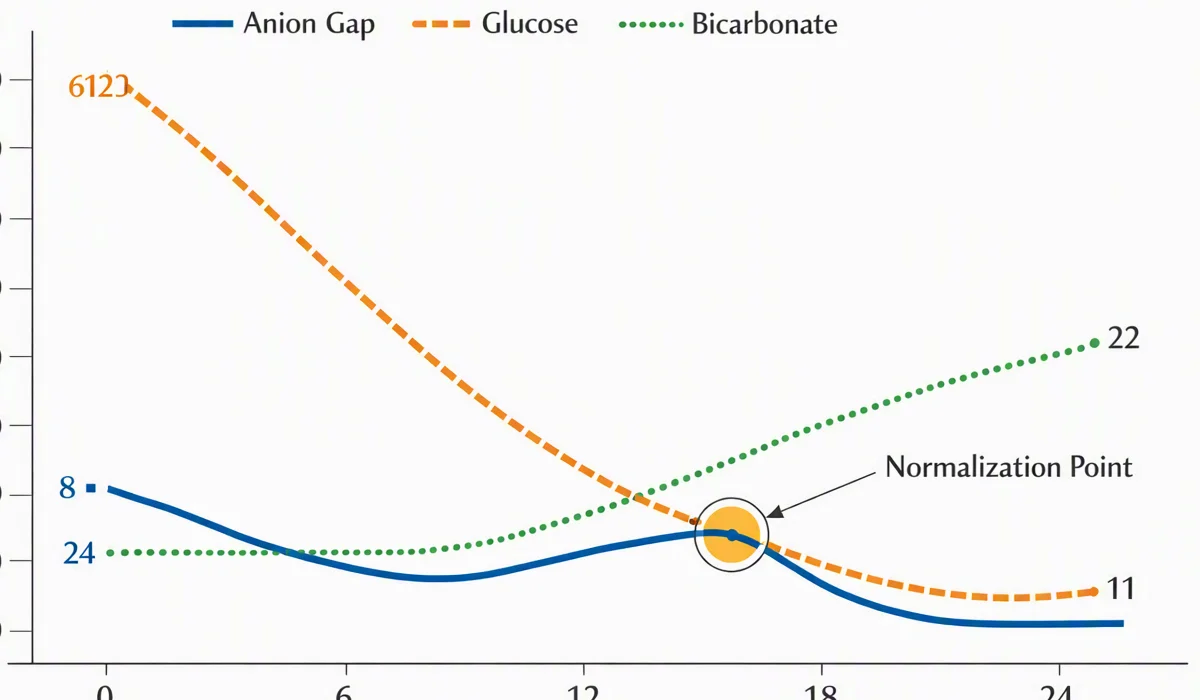
Some labs include potassium, but many do not. The precise reference range depends on the lab method and analyzer, so the number should always be read in light of the specific lab’s serum chemistry reporting. A value that is normal in one system may be slightly different in another.
Because the test is a form of metabolic acidosis screening, it is best used as part of a broader blood chemistry panel, not in isolation. The anion gap does not diagnose a disease by itself. Instead, it helps identify whether there may be occult acidosis or another hidden process affecting the blood chemistry.
Why bicarbonate can stay normal
A normal bicarbonate level doesn’t always indicate the body’s acid-base state is normal. Bicarbonate can stay in range because of compensation, the timing, or a mixed acid-base disorder. This is one reason the anion gap can be abnormal even when bicarbonate appears comforting.
In early disease, the body may have already started a compensatory mechanism before bicarbonate falls sufficiently to be flagged low. For example, a patient with developing acid production may still have a normal bicarbonate because the kidneys and lungs are temporarily working to preserve acid-base balance. That physiologic compensation can create a seemingly normal result.
A normal bicarbonate can also occur when two disorders cancel each other out. For instance, metabolic acidosis may lower bicarbonate while respiratory alkalosis pushes the pH in the other direction. In that setting, the bicarbonate may look near normal even though the overall pattern is abnormal. This is classic mixed acid-base disorder physiology.
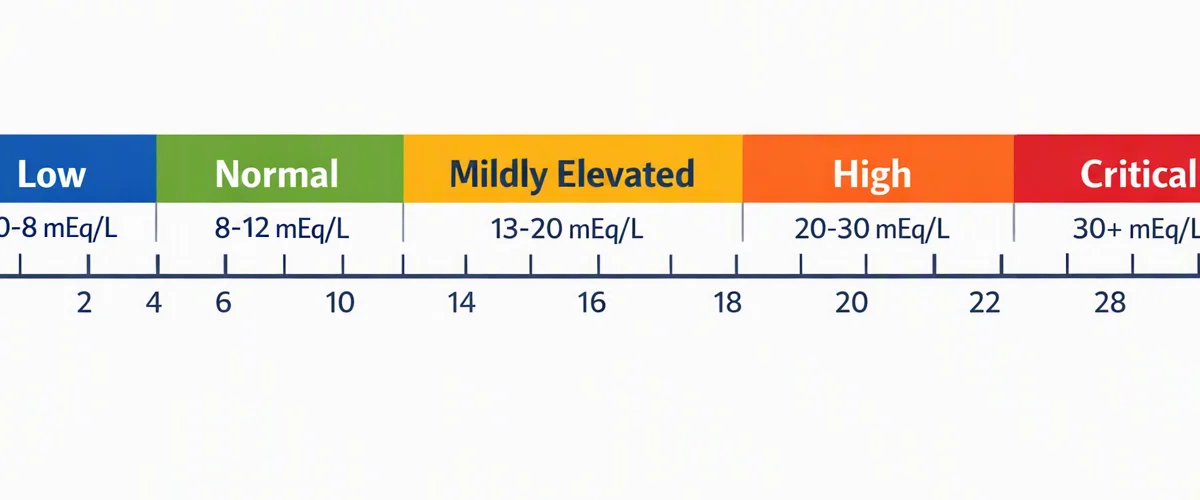
Because bicarbonate is part of the anion gap equation, a normal value can mask a change in the distribution of acids and bases. The result may still point to altered serum albumin, excess acids, or another metabolic process. That is why the clinical interpretation should not end with bicarbonate alone.
When reading a lab result, think in terms of the whole picture. A normal bicarbonate with a high gap may be an early warning sign that the body is losing its buffering reserve. The number may not appear striking yet, but it can still be an important diagnostic clue.
How to determine and interpret the anion gap
An anion gap calculator can accelerate the review and reduce calculation mistakes, especially when evaluating multiple laboratory values. The calculator typically uses sodium, chloride, and bicarbonate from the basic metabolic panel or similar blood chemistry panel. This is useful when the goal is fast clinical interpretation at the bedside or in a chart review.
Still, the calculation is only the starting point. A low albumin level can lower the measured gap because albumin is a major unmeasured anion. If albumin is reduced, the patient may have a deceptively normal or only mildly elevated gap despite real acid accumulation. That is why albumin correction matters.
The albumin-corrected anion gap adjusts the result so the clinician can better estimate the true burden of unmeasured acids. This is especially useful when the albumin level is abnormal, because low serum albumin can hide a clinically important high-gap process. In practical terms, a corrected value may reveal a high anion gap that was missed on the uncorrected number.
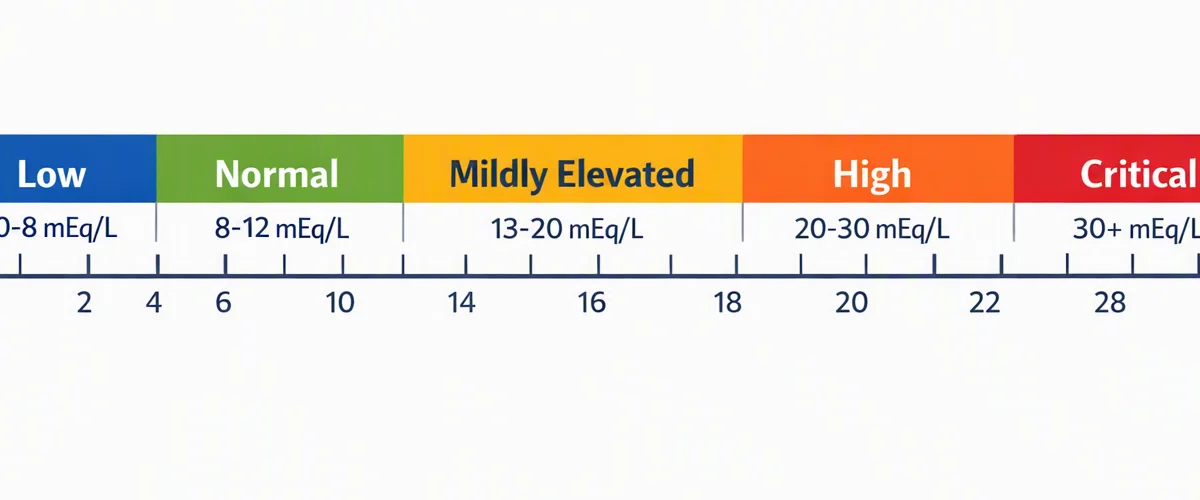
The reference range for the anion gap varies by laboratory method, so interpretation should always be aligned with the local report. Some labs use a narrower normal range than others, and the analyzer can influence the result. If the number is close to the border, look at the clinical context, repeat testing if needed, and confirm with related studies.
Using an anion gap calculator is especially useful when you want to compare the uncorrected and corrected results side by side. That comparison can reveal whether the patient has true excess acid, low albumin, or both. In many cases, the corrected value is the better marker of overall metabolic status.
How to interpret patterns when bicarbonate is normal
With normal bicarbonate, the behavior of the gap becomes the key clue. A normal bicarbonate can still coexist with a high anion gap, a normal anion gap, or a combined pattern. The challenge is determining whether the lab result reflects an early disorder, a compensated state, or a hidden second problem.
A high anion gap with normal bicarbonate may point to early acid accumulation before buffering is used up. This can happen before classic metabolic acidosis becomes clear. In that case, the anion gap is acting as an early diagnostic clue even though bicarbonate has not yet fallen.
A normal anion gap with normal bicarbonate is often calming, but not always conclusive. It may still occur if the patient has a compensated disorder, a mild process, or a laboratory issue. In some situations, a hidden second disorder keeps bicarbonate in range even as another abnormality is present.
The delta gap is useful when the gap is elevated and bicarbonate is not as low as expected. It helps determine whether there is only a high-gap process or whether a second metabolic process is present. If the delta gap suggests mismatch, think about a mixed acid-base disorder rather than assuming a single diagnosis.
A practical approach to view these patterns is:
- High gap + normal bicarbonate: possible early disease, compensation, or mixed disorder. Normal gap + normal bicarbonate: may be normal, but still review context and trends. High gap + low bicarbonate: more consistent for high-gap metabolic acidosis. Borderline gap + normal bicarbonate: review albumin, repeat testing, and the rest of the clinical picture.
The central point is that normal bicarbonate does not automatically rule out a clinically meaningful acid-base problem. The gap can be the first sign that the chemistry is shifting. That makes it especially valuable for metabolic acidosis screening and broader acid-base assessment.
Frequent causes of an elevated anion gap with normal bicarbonate
A number of conditions can cause a high anion gap before bicarbonate becomes elevated. The main causes are lactic acidosis, ketoacidosis, renal failure, and contact with toxic alcohols. These causes can create an early rise in unmeasured acids while bicarbonate still appears normal or near normal.
Lactic acidosis can develop when tissues are under pressure, underperfused, or not using oxygen effectively. During the initial phase, the anion gap may rise before the bicarbonate drops much. The lab pattern may be hard to detect, so the gap can be a helpful clue when symptoms suggest systemic illness.
Ketoacidosis may show a similar-looking pattern. Ketones are unmeasured anions, so the gap can rise as ketone production increases. Depending on timing, hydration, and respiratory compensation, bicarbonate may still be normal or only slightly changed.
Renal failure can also increase the gap because the kidneys are less able to clear acids and maintain electrolyte balance. In some cases, the initial lab change is an elevated gap before the bicarbonate clearly falls. Trend interpretation matters because worsening kidney function may be slow.
Toxic alcohols are another important cause because they generate organic acids that increase the gap. In these cases, the anion gap may be a key warning sign even if bicarbonate is not yet severely abnormal. Because the clinical consequences can be serious, this pattern should prompt careful review of history, exposure risk, and other labs.
This matters because they can represent occult acidosis before the expected acid-base profile appears. A normal bicarbonate should not end the evaluation when the gap is high and the clinical picture suggests a problem. Instead, it should prompt a more careful look at timing, associated symptoms, and repeat testing.
When a normal anion gap can still matter
A standard anion gap is often interpreted as reassuring, but it still matters in several scenarios. The first is possible lab error, which can happen from specimen issues, analyzer variation, or transcription mistakes. If the result does not fit the patient’s symptoms, repeat testing may be necessary.
The albumin level is another cause a normal gap may be misleading. Low albumin can decrease the gap and mask an otherwise elevated value. Without considering albumin, the interpretation may miss the real acid burden. This is why the albumin-corrected anion gap is often more informative than the uncorrected number.
Respiratory alkalosis can also complicate interpretation. A patient may hyperventilate and lower carbon dioxide while the bicarbonate remains normal early on, which can mask the true acid-base pattern. In some cases, this creates a confusing result unless the full acid-base picture is reviewed.
Most importantly, the result must be interpreted in clinical context. Symptoms, medication use, kidney function, nutrition, and recent illness can all affect the result. The anion gap is not just a number; it is part of a broader clinical interpretation that includes the patient’s history and current condition.
A normal gap does not fully exclude a metabolic problem, especially if the patient has concerning symptoms or a known risk factor. Looking at trends and related labs often reveals more than a single isolated result. In other words, the number is a tool, not the diagnosis.
Stepwise approach to reading the test result
Begin with the basic metabolic panel and locate sodium, chloride, and bicarbonate. This gives you the raw data needed for the anion gap calculation. When using an anion gap calculator, confirm that the numbers entered match the official report.
After that, check the bicarbonate and carbon dioxide value together with the rest of the panel. As bicarbonate is a proxy for acid-base buffering, a normal result can be comforting only if the rest of the pattern also fits. If the numbers do not make sense together, consider timing, compensation, or a mixed problem.
Then evaluate the gap against the lab’s reference range. If it is elevated, ask whether the patient could have lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. If albumin is low, calculate the albumin-corrected anion gap so you do not underestimate the abnormality.
If the gap is elevated but bicarbonate remains normal, consider the patient has early disease, a mixed acid-base disorder, or a compensatory state. At this point a blood gas can add important detail. The blood gas helps verify pH and whether carbon dioxide is low or high.
Use the pH to define the direction of the problem. If the pH is low, the patient may have acidemia even if bicarbonate is not yet reduced. If the pH is normal, the pattern may still indicate competing processes, so further review is needed. If the pH is high with an elevated gap, consider respiratory alkalosis or another process is masking the metabolic issue.
Finally, put the numbers into a complete clinical assessment. Review medication use, kidney function, glucose, lactate, ketones, toxin exposure, and any signs of infection or shock. The best interpretation comes from combining the lab result with symptoms, exam findings, and trend data.
When should you seek prompt evaluation
Certain anion gap abnormalities require urgent attention, especially when they occur with concerning symptoms. Fresh or worsening confusion, shortness of breath, marked weakness, chest pain, vomiting, or dehydration can signal a major metabolic problem. These findings should not be ignored merely because bicarbonate is normal.
Urgent evaluation is also appropriate when the person appears to have severe illness, such as sepsis, major kidney injury, poisoning, or uncontrolled diabetes. In these settings, a high gap may be an initial warning of deteriorating acid-base balance. Waiting for bicarbonate to fall can delay care.
Get timely medical assessment if the abnormal gap is recent, rising, or unexplained. Rechecking the labs may confirm whether the abnormality is ongoing or due to lab error. If the pattern suggests lactic acidosis, ketoacidosis, renal failure, or toxic alcohol exposure, timely treatment matters.
When in doubt, use the lab result as one piece of the full picture. A normal bicarbonate does not guarantee safety if the overall pattern suggests an acid-base problem. The right next step is often further evaluation, not assurance alone.
FAQ
Can you have an elevated anion gap with normal bicarbonate?
Indeed. An elevated anion gap can appear before bicarbonate falls, particularly in early disease, during compensation, or when a mixed acid-base disorder is present. That is why a normal bicarbonate does not automatically rule out an serious problem.
Does a normal bicarbonate rule out metabolic acidosis?
No. Normal bicarbonate does not fully rule out metabolic acidosis, especially if there is compensation or a second https://anion-gap-values752.raidersfanteamshop.com/how-chloride-shift-influences-the-anion-gap disorder affecting the result. The pH, blood gas, and anion gap help show whether the acid-base balance is actually abnormal.
How does low albumin affect the anion gap?
Low albumin lowers the measured anion gap because albumin is a major unmeasured anion. This can hide a true high anion gap disorder, which is why the albumin-corrected anion gap is important when albumin is reduced.
What is the difference between high anion gap and normal anion gap?
A elevated anion gap suggests extra unmeasured acids in the blood, such as associated with lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. A typical anion gap usually means there is not a significant accumulation of unmeasured acids, although context and albumin still matter.
When should an abnormal anion gap be checked again or urgently evaluated?
It should be reassessed if the result does not align with the clinical picture or if lab error is possible. Urgent evaluation is warranted when symptoms such as confusion or shortness of breath are present, or when severe illness, poisoning, kidney failure, or uncontrolled metabolic disease is suspected.