Why the anion gap Reflects
The anion gap is a calculated value that assists clinicians judge metabolic acidosis and other changes in electrolytes. It reflects the difference between routinely measured cations and anions in the blood, mainly using the electrolyte panel. In practice, the anion gap is a useful shortcut for detecting whether unmeasured acids may be accumulating in the body.
An anion gap calculator streamlines this process by converting the available lab values into a single number that aids diagnostic interpretation. Because the calculation depends on measured ions rather than direct acid detection, it acts as a marker of acid-base balance rather than a diagnosis by itself.
Most often, the anion gap is used to help differentiate high anion gap metabolic acidosis from normal anion gap metabolic acidosis. A high value may indicate the presence of organic acids such as lactate or ketones, while a normal value may imply bicarbonate loss or impaired renal handling of acid. The result should always be interpreted with the full clinical context and not as an isolated finding.
How to Operate an Anion Gap Calculator
An anion gap calculator typically requires three values: serum sodium, serum chloride, and serum bicarbonate. These values come from standard serum electrolytes testing. When the data is entered, the calculator uses the standard calculation formula:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)Some calculators may include potassium, but the usual clinical version excludes it. The reason this formula works is that measured sodium represents cation, while chloride and bicarbonate are the main measured anions. The gap indicates unmeasured ions, including albumin and other negatively charged proteins, organic acids, and various solutes.
To use the calculator correctly, make sure the lab values are from the same draw when feasible. Differences in timing can change the result, especially if the patient has a changing acid-base status. A single number should be read in combination with symptoms, medication use, renal function, and other laboratory findings.
What Makes Albumin Changes the Anion Gap
Albumin acts as one of the key unmeasured anions in blood. Because it carries a negative charge, it plays a major role to the anion gap. When serum albumin is low, the reported anion gap can appear misleadingly normal or barely increased, even when a real acid-base problem exists.
This is why hypoalbuminemia matters so much in clinical interpretation. If a patient has low albumin, the body has fewer negatively charged proteins to support the gap. That reduction can mask metabolic acidosis, especially in very anion gap in chronic kidney disease sick patients where the acid burden may be substantial.
The effect is tied to protein charge. As albumin falls, the body may respond with higher measured chloride or other shifts in serum electrolytes to preserve electroneutrality. The result is a reduced apparent gap, even if unmeasured acids are present. This is the reason albumin correction is often needed for more precise assessment.
Corrected Albumin Anion Gap Formula
The albumin-based corrected anion gap adjusts the measured gap to factor in low albumin in serum. A widely used correction formula is:
Corrected anion gap = measured anion gap + 2.5 × (4.0 - albumin in g/dL)In this method, normal albumin is generally considered 4.0 g/dL. For each 1 g/dL drop below typical, the anion gap is adjusted upward by about 2.5 mEq/L. This compensation factor estimates the contribution of albumin to the value and helps uncover a hidden high anion gap.
For example, if the measured gap is 10 and albumin is 2.0 g/dL, the corrected value becomes 10 + 2.5 × 2 = 15. That may move the result from a seemingly unremarkable range into a more concerning one. This is why albumin correction can change both diagnosis and treatment decisions.
Many tools integrate the basic calculator with albumin-based correction so the clinician can see both the original and adjusted values. That dual view boosts clinical utility, especially when the patient has low albumin from illness, inflammation, or poor nutrition.
Understanding Normal, High, and Low Anion Gap Findings
A normal anion gap is usually interpreted using the lab’s normal range, which can change by method and institution. In broad terms, a normal result suggests that the balance between measured cations and anions is in the expected range. However, a normal value does not automatically rule out acid-base disturbance, especially if albumin is low or if there are mixed disturbances.
A increased anion gap metabolic acidosis suggests presence of unmeasured acids. This pattern is classically associated with lactate, ketones, and retained acids in kidney dysfunction. It often calls for further testing for the underlying cause.
A decreased anion gap is less common and is often overlooked. It may occur when albumin is low, when there is excess positively charged protein, or when there is an analytical problem. Although a low value is not always dangerous, it should not be ignored because it can reveal important underlying disease or error.
Frequent Reasons of Raised Anion Gap
One major of the leading factors of an raised anion gap is lactic acidosis. Under these circumstances, lactate accumulates when oxygen transport or utilization is reduced. Sepsis, shock, severe hypoperfusion, and certain medications can all play a role. Because lactate is an unmeasured anion, the gap goes up as its concentration increases.
Ketoacidosis is a further classic cause. In diabetic ketoacidosis, starvation ketosis, or alcoholic ketoacidosis, ketones rise and raise the gap. In these situations, the acid burden may be significant even before the bicarbonate level falls dramatically.
Kidney failure can also cause elevated values because the kidneys cannot eliminate acids normally. With worsening kidney impairment, acids collect and bicarbonate may decrease. This is one reason the anion gap is often reviewed alongside creatinine, blood urea nitrogen, and the overall metabolic profile.
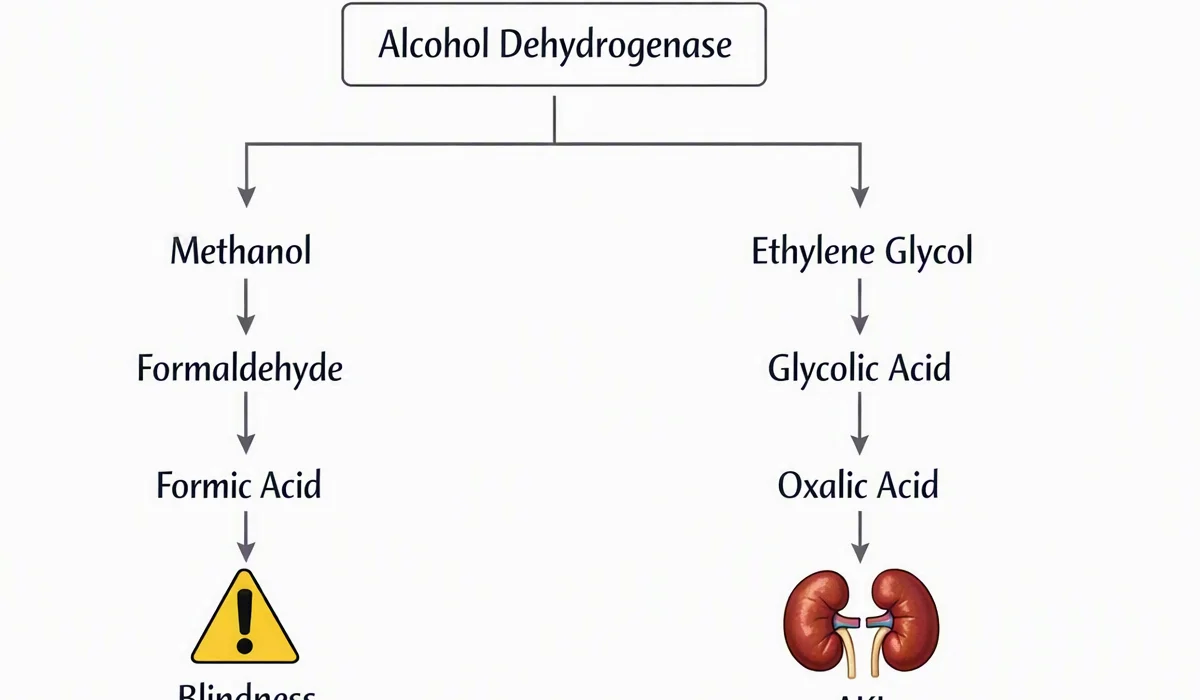
Other factors may include toxins, medications, and mixed disorders. Still, lactic acidosis, ketoacidosis, and renal failure remain among the most significant explanations for a high result.
Common Sources of a Low Anion Gap
A primary cause to consider is lab error. A slight error in sodium, chloride, or bicarbonate measurement can greatly affect the calculated value. If the result seems inconsistent with the clinical picture, repeating the test is often a useful first step.
Hypoalbuminemia is among the most frequent true sources of a low anion gap. Because albumin is a key unmeasured anion, low levels reduce the apparent gap. This makes albumin correction very important when reviewing an electrolyte panel in hospitalized or chronically ill patients.
Paraproteinemia can also lower the gap. In disorders with excess positively charged proteins, such as some monoclonal gammopathies, the measured balance shifts. It may appear that there are fewer unmeasured anions because the abnormal proteins affect the electrical distribution. A low gap in this setting can be a clue that deserves additional workup.
Less commonly, certain medications or analytical interferences can contribute. But in everyday practice, lab error, hypoalbuminemia, and paraproteinemia are the main considerations.
When to Apply Albumin Correction in Clinical Practice
Albumin correction is especially useful in critical care, where patients often have challenging acid-base disorder patterns and low serum albumin. In this setting, relying on the uncorrected number alone can overlook a meaningful elevation in the gap. That matters because treatment may depend on identifying the true source of acidosis.
It is also valuable when a patient has sepsis, malnutrition, liver disease, nephrotic syndrome, or fluid overload, all of which may reduce albumin. In these cases, the corrected result provides more accurate clinical interpretation than the raw number. It can also help distinguish a truly normal gap from a masked high gap state.
As a practical rule, if albumin is below normal and the clinical concern is unexplained acidosis, correction should be seriously considered. The calculator becomes more valuable when it is used as part of a more complete assessment rather than as a standalone metric.
Limitations of the Anion Gap Calculator
Even a properly designed anion gap calculator has limits. The biggest is the dependence on the lab’s reference range and analyzer method. Different measurement platforms can yield different baseline values, so what looks abnormal in one system may be acceptable in another.
Measurement error can also affect the result. Small inaccuracies in serum sodium, serum chloride, or serum bicarbonate can shift the calculation noticeably. In addition, not all causes of acidosis create a high gap, and mixed disorders can blur the pattern.
Clinical context remains essential. A normal or corrected value does not exclude illness, and a high value does not identify the cause by itself. The result should always be interpreted with symptoms, vital signs, kidney function, lactate, ketones, medication exposure, and overall clinical interpretation. The calculator is best viewed as a decision-support tool, not a replacement for judgment.
FAQ About the Anion Gap Calculator
What does an anion gap calculator meant for?
An anion gap calculator helps to estimate the anion gap from basic lab values and help evaluate metabolic acidosis. It is especially helpful chronic kidney disease high anion gap for identifying high anion gap metabolic acidosis and for aiding clinical interpretation of an abnormal electrolyte panel.
How do you correct the anion gap for albumin?
Albumin correction is usually done by adding about 2.5 mEq/L to the measured anion gap for each 1 g/dL of albumin below normal albumin of 4.0 g/dL. This yields an albumin-corrected anion gap that more closely represents the true acid-base status when hypoalbuminemia is present.
Why can low albumin affect the anion gap?
Serum albumin carries negative protein charge and makes a major contribution to the gap. When albumin is low, fewer unmeasured anions are present, so the measured value may fall even if the patient still has an underlying acid burden. This can make the gap look less abnormal than it really is.
What can a high anion gap mean?
A high result often indicates metabolic acidosis from unmeasured acids such as lactate or ketones. Common causes include lactic acidosis, ketoacidosis, and renal failure. The exact meaning depends on the patient’s history, other labs, and overall clinical context.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap can still occur with normal anion gap metabolic acidosis, such as bicarbonate loss states. It can also appear normal when hypoalbuminemia masks a true elevation, which is why albumin correction is important for accurate anion gap interpretation.