What the anion gap Measures
The anion gap serves as a practical approach to identify unmeasured ions in the blood and to guide acid-base balance during a clinical workup. It’s typically derived from serum electrolytes, especially serum sodium, serum chloride, and serum bicarbonate. As these values shift in specific ways, the anion gap can reveal a hidden metabolic disturbance that would otherwise be missed on a basic chemistry panel.
In routine care, clinicians use the anion gap as a diagnostic marker for acid accumulation. A elevated value suggests that unmeasured acids are present in excess, often pointing toward metabolic acidosis. This makes the calculation particularly useful as an interpretation guide when reviewing an ill patient, a lab screening result, or a suspected electrolyte imbalance.
The basic anion gap formula typically subtracts chloride and bicarbonate from sodium. Some versions also include potassium, but the standard approach excludes it for simplicity and consistency. An anion gap calculator streamlines this step, helping clinicians quickly calculate anion gap values and consider the bigger question: what underlies the abnormality?
Because the calculation is based on measured ions, it is not a complete picture of physiology. Instead, it is a fast and useful approximation that supports laboratory assessment and more detailed acid-base interpretation. When the result is elevated, it often signals an elevated anion gap state that requires a closer look at renal function, perfusion, toxin exposure, and inherited metabolic disease.
Why Methylmalonic Acidemia Raises the Anion Gap
Methylmalonic acidemia is an acid-related metabolic disorder and an inherited metabolic disorder in which the body cannot properly break down certain metabolites, leading to the buildup of organic acids. That buildup creates acid buildup and commonly leads to a high anion gap metabolic acidosis. In this setting, the anion gap becomes a indicator to the underlying biochemical problem rather than just a number on a report.
The main problem is that methylmalonic acid along with related compounds build up in the bloodstream. These acids deplete buffering capacity, reduce bicarbonate levels, and contribute to an excess of unmeasured anions. Therefore, the anion gap often increases alongside the severity of the acid-base disorder. For this reason a calculator can be helpful in identifying the pattern early, especially when the patient is very sick and the presentation is vague.
Within methylmalonic acidemia, the overall picture may indicate a metabolic emergency. Affected patients can develop vomiting, poor feeding, lethargy, dehydration, or encephalopathy, convert AG mEq to mmol and the test results may show an elevated anion gap long before the full diagnosis is confirmed. The biochemical pattern usually indicates accumulation of toxic metabolites, decreased energy metabolism, and secondary systemic stress. That is why an anion gap calculator can be a valuable initial step in interpretation, but not the last step in diagnosis.
The association between the measured gap and the underlying process is greatest when the presentation includes acidosis along with further supportive findings. Even so, the anion gap alone does not establish methylmalonic acidemia. It serves as a clinical correlation tool that helps clinicians detect a profile consistent with an organic acid increase and move toward targeted workup.
How to Operate an Anion Gap Calculator
To use an anion gap calculator, input the key serum electrolytes: serum sodium, serum chloride, and serum bicarbonate. Many calculators also allow entry of potassium and albumin. The calculator uses the specified formula and shows the observed gap, which can then be compared with the expected range for the lab.
With potassium included, the formula may produce a slightly higher value. In many clinical settings, however, potassium is omitted because it contributes less to everyday decision-making and can vary between institutions. The more important step is to recognize whether the result suggests an elevated anion gap and whether that elevation aligns with the rest of the patient’s picture.
Albumin matters because it is a major unmeasured anion. Low albumin can make the anion gap appear falsely normal or only mildly elevated. That is why many clinicians apply albumin correction to estimate a corrected anion gap. This is especially important in patients with malnutrition, inflammation, liver disease, or prolonged illness, where hypoalbuminemia can mask the degree of acidosis.
A practical step-by-step approach looks like this:
- Enter the available serum electrolytes into the calculator. Assess whether the result indicates a high or normal gap. Check albumin and apply albumin correction if needed. Compare the result with the clinical setting and other labs. Consider the number as part of broader acid-base interpretation, not as a standalone answer.
When done correctly, the calculator helps organize the workup and supports a more accurate assessment of acid-base balance. It is most useful when paired with symptoms, kidney function, ketones, lactate, and a blood gas.
Explaining Increased Anion Gap Values
A elevated anion gap metabolic acidosis indicates that unmeasured acids are accumulating. In the differential, the typical categories include lactic acidosis, ketoacidosis, and toxin exposure. These conditions can overlap with methylmalonic acidemia or mask it, so interpretation should always be clinical rather than mechanical.
anion gap in chronic kidney diseaseLactic acidosis may occur with hypoperfusion, shock, hypoxemia, seizures, or severe illness. It produces excess lactate, which widens the gap. Ketoacidosis occurs in diabetes, prolonged fasting, or starvation states, and the ketone bodies add to the elevated gap. Both can coexist with other metabolic abnormalities, making the final pattern less straightforward than a single diagnosis.
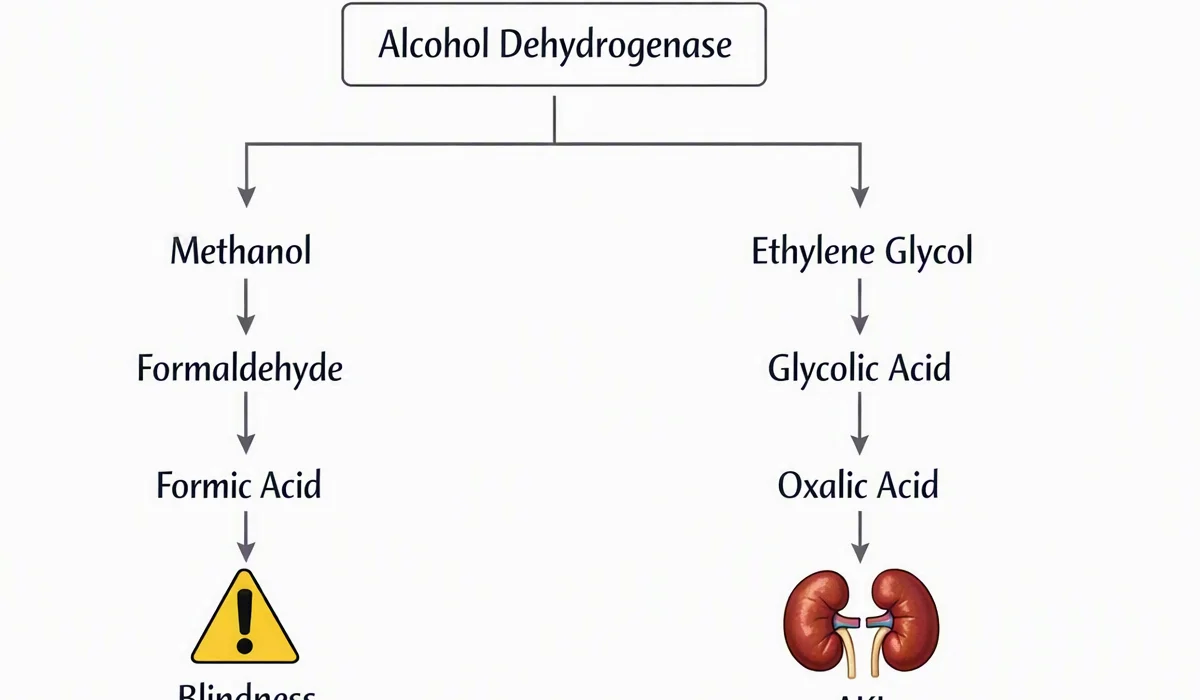
Toxin exposure should also be kept in mind when the gap is high. Salicylates, toxic alcohols, and other poisons may generate a substantial acid burden. In suspected ingestion, the anion gap is a helpful clue but not the endpoint. Osmolal gap testing, toxicology studies, and serial blood gas data may be needed for a thorough picture.
For methylmalonic acidemia, the key point is that a high anion gap can be a sign of organic acid buildup, but not every elevated gap is caused by an organic acidemia. A careful assessment helps separate the biochemical pattern from the underlying cause. The calculator can identify the abnormality, but interpretation requires the full context of illness severity, nutrition status, renal function, and timing of collection.
Adjusting the Anion Gap & Clinical Setting
Initial anion gap values can be inaccurate unless the overall acid-base disturbance is evaluated. This is where correction for albumin becomes relevant. As albumin is an anion, low levels reduce the baseline gap. A patient with marked acidosis and hypoalbuminemia may therefore show a falsely normal result unless the value is corrected.
Adjusting for albumin improves the utility of the anion gap calculator and makes the number more representative of true acid burden. This matters especially in critically ill patients, where low albumin is common and compensatory metabolism may somewhat offset pH changes. A normal pH does not eliminate acidosis if compensation is present.
For this reason blood gas analysis is such an important companion test. A blood gas can establish pH, bicarbonate status, and compensatory respiratory changes. Combined with the corrected gap, it helps define whether the patient has primary metabolic acidosis, a superimposed respiratory process, or a complex acid-base disturbance.
Practically speaking, clinicians should avoid interpreting the anion gap in isolation. The most accurate approach integrates albumin, serum chemistry, blood gas analysis, symptoms, and time course. That complete review can separate an acute metabolic emergency from a chronic compensated state and can prevent under-recognition of severe disease.
Laboratory Results in Methylmalonic Acidemia
A number of lab findings help support the diagnosis of methylmalonic acidemia. The clearest is high methylmalonic acid, which indicates the underlying enzymatic block and confirms the presence of excess abnormal metabolites. This finding often is associated with a high anion gap state, but the magnitude of the gap can fluctuate depending on hydration, nutrition, and concurrent illness.
Cobalamin deficiency is a key related consideration because vitamin B12 metabolism is tightly linked to methylmalonic acid handling. In some patients, low B12 or impaired cobalamin processing plays a role in the biochemical picture. This is why methylmalonic acidemia and cobalamin-related disorders are often worked up together during a laboratory assessment.
Ammonia may also be elevated, especially during decompensation. Hyperammonemia can aggravate neurologic symptoms and raise the concern for a metabolic crisis. Likewise, ketones may be present as the body shifts toward alternative fuels during stress or inadequate intake. These findings strengthen the suspicion of a serious inherited metabolic disorder.
When all these results are viewed together, the pattern stands out more clearly: elevated methylmalonic acid, possible cobalamin involvement, increased ammonia, and ketosis can accompany a high anion gap. The result is a biochemical pattern that clearly supports further metabolic testing and urgent clinical correlation.
Frequent Alternative Diagnoses
Various conditions can look like methylmalonic acidemia on early assessment. Propionic acidemia is one of the most important because it is another organic acidemia with shared features, including acidosis, ketosis, and an high gap. Distinguishing these conditions usually requires specific biochemical and genetic evaluation rather than a one electrolyte panel.
Renal failure is another common reason of high anion gap acidosis. When kidney function declines, acids accumulate and unmeasured anions rise. In this setting, the anion gap may be elevated for reasons unrelated to an inborn error of metabolism, so renal markers and the overall clinical context are important.
Sepsis can also produce a high-gap picture through lactic acidosis, poor perfusion, and multiorgan stress. Because sepsis can present with nonspecific symptoms and rapid decompensation, it can overlap clinically with metabolic disease. A clinician evaluating a patient with suspected methylmalonic acidemia should always consider infection as a trigger or an alternate explanation.
More broadly, the category of inborn errors of metabolism includes many conditions that present with acidosis, hyperammonemia, and neurologic changes. Anion Gap Calculator is useful for interpreting the acid-base pattern, but the differential diagnosis must remain extensive until confirmatory studies narrow it down.
When the Anion Gap May Be Misleading
Even though the anion gap is useful, it is not infallible. A patient with serious disease may still show a normal anion gap if the abnormality is hidden by low albumin, early sampling, or concurrent alkalinizing processes. In methylmalonic acidemia, this can happen if the patient has been given fluids, is partially treated, or is in a milder phase of illness.
Mixed acid-base disorders are some of the key pitfalls. For example, a patient may have metabolic acidosis from acid accumulation and a concurrent respiratory alkalosis from hyperventilation. The pH can look almost normal even though the underlying disturbance is important. Blood gas interpretation is therefore crucial.
Hypoalbuminemia can lower the apparent gap to the point to hide the severity of the disorder. This is why albumin correction plays such a key role. If albumin is low and the corrected result becomes obviously abnormal, the concern for an organic acid process rises substantially.
Laboratory variation can also affect the result. Minor variations in analyzer method, specimen handling, or repeat sampling can change the number a bit. For that reason, a single borderline value should not be overinterpreted. Trend data, the clinical picture, and repeat testing are often more revealing than one isolated result.
In short, the anion gap is a helpful indicator, not a diagnosis. The best interpretation comes from integrating the calculator output with blood gas analysis, albumin status, symptoms, and the broader biochemical pattern.
Frequently Asked Questions
How does an anion gap calculator help in methylmalonic acidemia?
An anion gap calculator helps by quickly identifying whether the patient has an elevated gap consistent with metabolic acidosis. In methylmalonic acidemia, this supports recognition of organic acid buildup and helps guide further testing. It is a useful screening tool, but it does not substitute for clinical evaluation or confirm the diagnosis on its own.
What anion gap formula should be used for serum electrolytes?
The most common anion gap formula is based on serum sodium minus the sum of serum chloride and serum bicarbonate. Certain formulas include potassium, but many clinical calculators omit it. The right option is the one that matches the laboratory and the clinician’s assessment method for serum electrolytes.
Can methylmalonic acidemia cause a normal anion gap?
Yes, it can. Methylmalonic acidemia can sometimes appear with a normal anion gap, especially if there is hypoalbuminemia, early disease, treatment effects, or a mixed acid-base disorder. For this reason the calculator should be paired with albumin correction and blood gas analysis.
Why is albumin correction important when interpreting the anion gap?
Albumin is a major unmeasured anion, so low levels can make the gap look falsely normal. Albumin correction helps estimate the true corrected anion gap and improves acid-base interpretation. This is especially important in illness, where hypoalbuminemia can mask a significant high anion gap metabolic acidosis.
Which other disorders can look like methylmalonic acidemia on an anion gap test?
Common mimics include propionic acidemia, renal failure, sepsis, lactic acidosis, ketosis, and other inborn errors of metabolism. Toxin exposure can also produce a similar pattern. The anion gap is helpful for identifying the biochemical pattern, but the final diagnosis depends on the whole laboratory and clinical picture.