What the Anion Gap Measures
The anion gap is a useful way to gauge the difference between measured electrolytes in the blood and the unmeasured ions that also affect acid-base balance. From a clinical standpoint, it is most valuable as a fast screen for metabolic acidosis and additional metabolic disturbances that may not be apparent from a single lab value. An anion gap calculator helps turn routine serum chemistry results into actionable diagnostic support at the bedside.
In its basic form, the anion gap represents the difference between positively charged and negative analytes reported on an electrolyte panel. The major measured components are serum sodium, serum chloride, and serum bicarbonate, with potassium sometimes included depending on the formula used. Because not all ions are directly measured, the gap can highlight patterns that suggest lactic acid accumulation, ketones, retained acids, or exposure to toxic substances.
From a physiologic perspective, the anion gap is not a diagnosis by itself. It is a triage and review tool that helps refine the differential diagnosis when laboratory results show an abnormal acid-base status. Used well, it supports prompt recognition of serious illness, faster confirmatory testing, and more focused bedside assessment.
Calculating the Anion Gap
The main calculation formula is easy to apply:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians and institutions also include potassium in the equation:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
Both formulas are used in practice, but the potassium-free version is more common because serum potassium is usually much smaller than sodium and may not meaningfully change interpretation in many cases. However, if your calculator includes potassium, it is important to know which reference range and formula the tool uses so that the result is interpreted correctly.
To use an anion gap calculator, add the serum values from the patient's lab report:
- Serum sodium Serum chloride Serum bicarbonate Potassium, if the chosen formula includes it
The result should then be checked against the lab's reference range. The range may vary depending on the analyzer, method, and potassium inclusion, so the same numeric result may be interpreted slightly differently across institutions. A strong bedside calculator should display the formula clearly and explain the context of the result rather than presenting it as an isolated answer.
For example: if sodium is 140, chloride is 104, and bicarbonate is 20, the potassium-free anion gap is 16. This may be normal or only mildly elevated depending on the local reference range and albumin level. This is why context matters as much as the math.
Recalculating the Anion Gap for Serum Albumin
Albumin is a major unmeasured anion in plasma, so changes in albumin can significantly affect the observed gap. In patients with hypoalbuminemia, the measured anion gap may look falsely normal or only slightly elevated even when clinically important acids are present. For that reason, many clinicians estimate a corrected anion gap to increase sensitivity.
The need for albumin correction is based in serum proteins: when albumin falls, the body loses a significant negatively charged component, and chloride may rise to maintain electrical neutrality. That compensation can hide a true high-gap process. In practice, a correction factor is applied to approximate the gap the patient would have if albumin were normal.
A commonly used approach is:
Corrected anion gap = measured anion gap + 2.5 x (4.0 - albumin in g/dL)
This formula is one of several accepted methods, and local practice may vary. The key point is not memorizing a single number but recognizing that low albumin can conceal metabolic acidosis. If the albumin is substantially reduced, corrected interpretation becomes especially important for accurate clinical decision support.
Example: a patient has a measured anion gap of 12 and albumin of 2.0 g/dL. The correction adds 5, yielding a corrected anion gap of 17. That shift can change the entire diagnostic direction, prompting attention to high-gap causes that might otherwise be missed.
How to Read High, Average, and Low Anion Gap Results
Analysis starts with the overall clinical context, then moves to the measured value, the albumin-adjusted value, and the linked acid-base profile. The anion gap is most useful when interpreted with pH, serum bicarbonate, and the rest of the metabolic panel.
High anion gap metabolic acidosis
A high gap usually suggests accumulation of unmeasured acids and raises concern for high anion gap metabolic acidosis. Common mechanisms include acid production, acid ingestion, or reduced clearance of organic acids. The key bedside question is whether the elevated gap explains the low bicarbonate and whether the patient also has another additional process.
A high gap should lead to a focused differential diagnosis, review of symptoms, medication and toxin exposure, AG calculator adding K and rapid assessment of severity. It may also warrant confirmatory testing such as lactate, ketones, arterial or venous blood gas, renal function testing, and toxicology studies.
Normal anion gap metabolic acidosis
A normal or near-normal result does not exclude metabolic acidosis. Normal anion gap metabolic acidosis often suggests loss of bicarbonate or failure to excrete acid with compensatory chloride retention. In these cases, the acid-base disorder is present even though the gap does not appear elevated. This is why an anion gap calculator should be used as part of a broader interpretation, not as a standalone screening endpoint.
Examples include gastrointestinal bicarbonate loss, renal tubular problems, and other causes of hyperchloremic acidosis. If the clinical setting suggests acidosis but the gap is normal, further analysis of bicarbonate, chloride, potassium, and blood gas values is essential.
Low anion gap
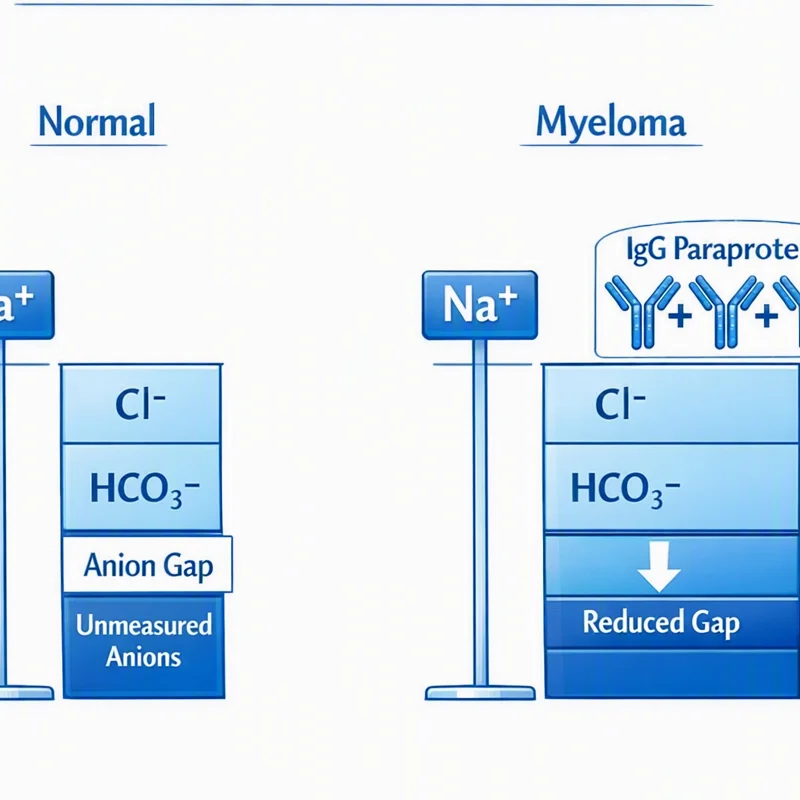
A low anion gap is less common but should not be ignored. It may reflect hypoalbuminemia, analytic issues, excess unmeasured cations, or uncommon paraprotein-related states. In some cases, the low value is an artifact; in others, it is a clue to a real disorder. Because of this, a low result warrants careful review of the laboratory results, albumin, and the possibility of laboratory error before making clinical assumptions.
In general, proper anion gap interpretation involves noting that both high and low values can be significant and that the result must be considered in the context of the patient’s acid-base disorders, fluid status, and other chemistry findings.
Typical Causes of an Abnormal Anion Gap
Several disorders are classic causes of an abnormal gap, especially when metabolic acidosis is present. What the calculator does well is identify patterns early and structure the next steps in the diagnostic workup.
Lactic acidosis is one of the most important causes of high-gap acidosis. It can occur with circulatory collapse, reduced blood flow, severe infection, seizures, hypoxia, and other states of impaired tissue oxygen delivery or utilization. Lactate is an unmeasured anion, so its accumulation can elevate the gap substantially.
Ketoacidosis is another important cause, often seen with diabetes, starvation, alcohol use, or other physiologic stressors. Ketone bodies contribute to the acid load and raise the anion gap, sometimes with rapid changes over time as treatment begins.
Renal failure can raise the gap because the kidneys are unable to excrete acids effectively. Uremic acids accumulate, and the serum chemistry may show a rising gap alongside worsening creatinine and bicarbonate abnormalities.
Toxic alcohols are critical not to miss. Ingestion of substances such as methanol, ethylene glycol, or related compounds can produce a high-gap metabolic acidosis and severe systemic toxicity. In these situations, the anion gap is part of urgent risk stratification, but it should be paired with confirmatory testing whenever possible.
Additional causes are possible, and mixed presentations are common. That is why the gap should be viewed as a clue rather than a conclusion. It helps narrow the differential diagnosis while further evaluation identifies the exact cause of the metabolic derangement.
Employing the Calculator in Clinical Decision Support
An effective clinical decision support tool should go beyond calculate a number. It should assist with bedside assessment, limit arithmetic errors, and allow clinicians to quickly connect the result with the next best action. In a fast-paced setting, the calculator becomes part of a larger diagnostic workflow that starts with laboratory results and ends with a more informed plan.
In day-to-day practice, anion gap in chronic kidney disease the anion gap calculator can be used for:
- Rapid screening for high-gap metabolic acidosis Recognition of patterns that suggest lactate, ketones, renal dysfunction, or toxin exposure Adjustment for hypoalbuminemia when hypoalbuminemia is present Trend monitoring across serial lab checks Helping with timely confirmatory testing
Because serum chemistry results are often available before the full clinical picture is clear, the calculator can help prioritize urgency. For example, an elevated corrected anion gap may strengthen concern for a serious metabolic process even before the source is identified. That is especially valuable when the patient is unstable, when bedside history is limited, or when the presentation is nonspecific.
As a bedside tool, the calculator should also reduce cognitive load. A well-designed interface turns multiple analytes into a simple output while still showing the underlying formula and correction factor. This helps ensure more confident interpretation without replacing clinical judgment.
Limitations, Pitfalls, and Good Practices
Even though it is useful, the anion gap has major drawbacks. The first is differences in the reference range. Multiple laboratories may use different assays or calculation conventions, and the presence or absence of potassium in the formula can alter what counts as normal. Consistently interpret the result using the same method the calculator uses.
Laboratory error is another common pitfall. Inaccurate chloride, sodium, or bicarbonate results can distort the gap and create confusing conclusions. If the number does not fit the clinical context, run the test again or review specimen quality before acting on the result alone.
Mixed acid-base disorders can also obscure interpretation. A patient may have a high-gap acidosis and a separate alkalosis, or a normal-gap acidosis plus a second process that masks the expected pattern. In these cases, the anion gap should be interpreted alongside pH, bicarbonate, respiratory compensation, and the overall serum chemistry profile.
Further best practices include:
- Assess albumin whenever the gap is unexpectedly normal or low Use the corrected anion gap when hypoalbuminemia is present Review current and prior values to detect change over time Evaluate whether the pattern matches the bedside story Use confirmatory testing when the abnormal result suggests serious disease
The goal is reliable anion gap interpretation, not just numerical output. A thoughtfully used calculator can enhance screening, support earlier diagnosis, and reduce the chance of missing a clinically important metabolic process.
Common Questions
How can you compute the anion gap using sodium, chloride, and bicarbonate?
Apply formula anion gap = sodium - (chloride + bicarbonate). Input the patient’s serum sodium, serum chloride, and serum bicarbonate into the calculator, then contrast the result with the lab’s reference range. Some calculations include potassium as well, so it is necessary to know which version is being used.
Why must the anion gap be corrected for albumin?
Albumin correction is necessary because albumin is a major unmeasured anion. If albumin is low, the measured gap may underestimate the true acid burden. Correcting for hypoalbuminemia helps reveal a hidden high-gap process and improves the accuracy of clinical interpretation.
What may a high anion gap indicate clinically?
A high value often suggests high anion gap metabolic acidosis from unmeasured acids. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result should prompt timely evaluation of the clinical context and consideration of confirmatory testing.
Can a normal anion gap still occur with metabolic acidosis?
Absolutely. Normal anion gap metabolic acidosis is a real disorder and often reflects bicarbonate loss with compensatory chloride retention. A normal result does not rule out metabolic acidosis, so interpretation should include pH, bicarbonate, chloride, and the broader clinical picture.
What are the common causes of a low anion gap?
A low anion gap may be caused by hypoalbuminemia, laboratory error, unusual increases in unmeasured cations, or certain protein abnormalities. If the result is unexpected, reassess the lab data, consider repeat testing, and assess whether albumin or other serum proteins explain the abnormality.