What the Anion Gap Measures
The anion gap is a helpful calculated value from the electrolyte panel that assists laboratory professionals support acid-base interpretation and broader serum chemistry review. It reflects the anionic difference between routinely measured cations and anions, frequently using serum sodium, serum chloride, and serum bicarbonate. Although the result is derived rather than directly measured, it provides meaningful insight into electrolyte balance and the patient’s physiologic state.
From a laboratory perspective, the anion gap is best viewed as a screening tool that offers diagnostic support rather than a standalone diagnosis. Changes in the gap can point to an acid-base disorder, especially metabolic acidosis, and may prompt closer review of the specimen, the analytical context, and the full chemistry profile. Because the value depends on several measured analytes, it is also sensitive to analytical variation and preanalytical factors that affect specimen integrity.
In routine practice, the anion gap helps link a chemistry result to a larger clinical picture. It can flag a possible metabolic disturbance, guide the need for reflex review, and assist with result interpretation when a panel appears discordant. For laboratory professionals, its value lies not only in the number itself, but in the pattern recognition it supports across the entire serum chemistry profile.
How to Use an Anion Gap Calculator
An anion gap calculator makes easier the calculation method by following the standard equation to the analytes entered from the electrolyte panel. In typical workflows, the user enters sodium, chloride, and bicarbonate values, and the calculator returns the derived gap immediately. This is useful for rapid review during laboratory analysis, validation, or post-analytic interpretation.
Before entering results, verify that the values are from the same specimen and the same reportable set. A discrepancy in sample timing or a specimen with compromised integrity can alter the final number. Good practice begins with checking the source data, ensuring that the values are consistent, and verifying whether the result should be interpreted against the local reference interval used by the laboratory.
A calculator is very helpful when reviewing multiple panels or when comparing current results with prior values. It supports faster identification of abnormal trends and can help the laboratory professional recognize whether the pattern is compatible with metabolic acidosis, high anion gap metabolic acidosis, or a possible nonpathologic shift. In practice, the calculator serves as a structured aid for acid-base interpretation and standardized reporting guidance.
For accurate use, remember these steps:
- Confirm the correct serum sodium, serum chloride, and serum bicarbonate values. Review for unit consistency and transcription accuracy. Assess whether the laboratory uses an uncorrected or albumin-adjusted approach. Read the output in context with the full electrolyte panel and associated findings.
Anion Gap Formula and Calculation Methods
The standard anion gap formula is usually written as the sodium value minus chloride plus bicarbonate, grouped together: Na − (Cl + HCO3). This gives the uncorrected anion gap, which is the usual value listed in many chemistry processes. Some laboratories also use a variant that includes potassium, but sodium-based calculation remains the usual starting point for routine review.
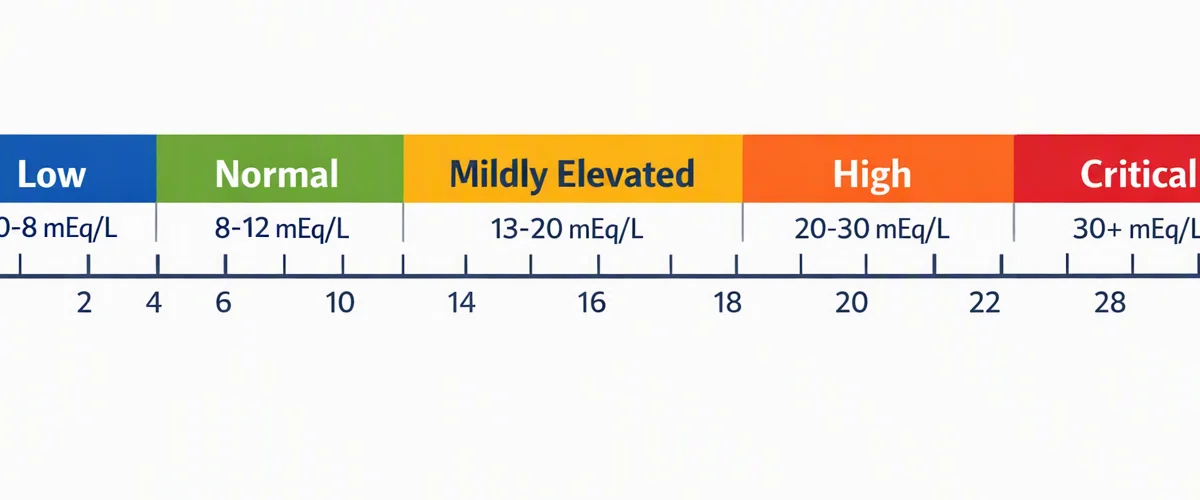
The calculated value should always be assessed relative to the laboratory’s reference range or reference interval, since method-specific differences and analyzer platforms can shift expected values. An interval that is valid for one instrument or population may not match another. For this reason, laboratory professionals should match the interpretation with local validated limits rather than applying a generic cutoff without review.
Albumin correction is a key part of the calculation conversation. Because albumin is a major unmeasured anion, reduced albumin can reduce the measured gap and obscure an underlying disturbance. The albumin-corrected anion gap helps adjust for this effect and can improve interpretive accuracy, especially when hypoalbuminemia is present. In those settings, a normal uncorrected value may not represent the true acid-base picture.
From a laboratory standpoint, the choice between uncorrected and corrected reporting should be guided by local policy, analytic capabilities, and clinician needs. A clear note in the report can improve clinical correlation, especially when the corrected value changes the interpretation from normal to abnormal. The corrected value is not a replacement for judgment, but it offers a more complete picture for laboratory analysis and downstream review.
Interpreting Elevated and Reduced Anion Gap Results
A high result is frequently associated with high anion gap metabolic acidosis, a finding that suggests accumulation of unmeasured acids. This pattern is a key indicator of metabolic acidosis and requires review of the rest of the chemistry profile, the patient context, and any available confirmatory testing. Typical causes include organic acid accumulation, impaired clearance, or toxin-related processes, depending on the broader clinical picture.
A low anion gap is uncommon and should prompt careful evaluation for analytic or physiologic explanations. Because the value is derived, a low result can reflect altered albumin concentration, increased unmeasured cations, or laboratory error. Before assigning meaning, laboratory professionals should verify the original measurements and consider whether specimen or instrument issues could explain the finding.
Assessment should center on pattern recognition rather than a single cutoff alone. A moderate elevation may be important in one context and less significant in another, particularly if the patient has an expected shift in acid-base disorder. Likewise, a low value may be actionable if it fits with other chemistry findings, but may also be a clue to reassess the dataset for preanalytical or analytic issues.
In laboratory practice, an abnormal anion gap should be interpreted as a result-pattern problem first and a disease label second.
When the result appears inconsistent with the rest of the profile, compare with prior values, verify instrument performance, and consider whether the discrepancy is due to laboratory error or a true change in the patient’s physiologic state. This approach supports more reliable result interpretation and better communication with the care team.
Common Causes of Abnormal Results
Several conditions are typically associated to an increased gap. Lactic acidosis is one of the most common causes and often indicates poor oxygen delivery, changed perfusion, or metabolic stress. Ketoacidosis can also elevate the gap due to the accumulation of ketone bodies, while renal failure may be involved through decreased acid removal and retention of unmeasured anions.
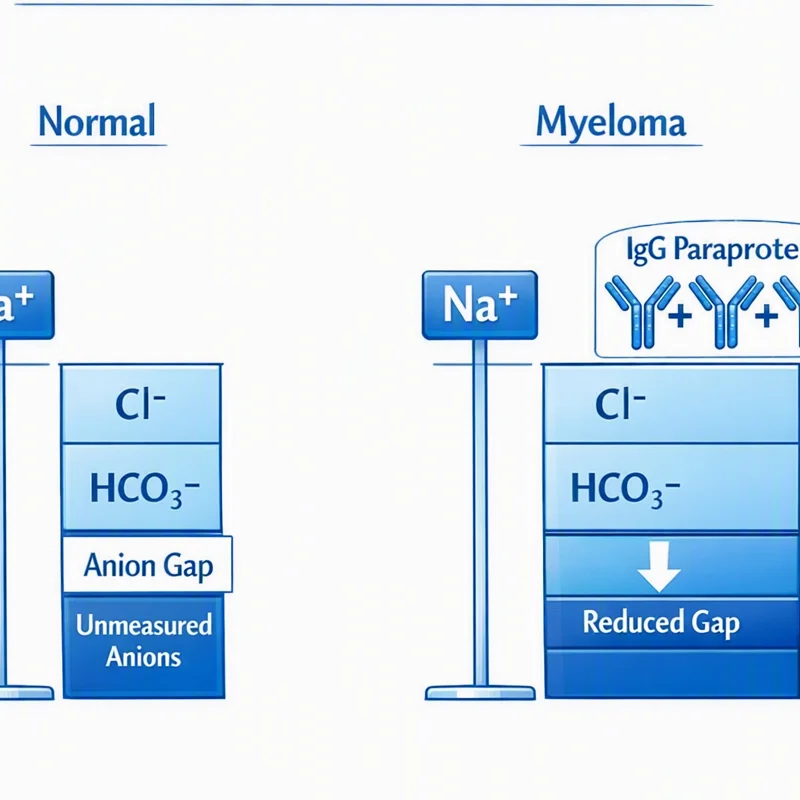
For lower values, hypoalbuminemia is among the most important considerations because low albumin reduces the measured gap. This is why the albumin-corrected anion gap is useful in clinical practice. If albumin is significantly reduced, the uncorrected value may appear normal or decreased even when the underlying metabolic picture is abnormal.
Additional abnormal patterns may be due to medication effects, specimen contamination, or odd electrolyte shifts. In a lab setting, it is helpful to consider a wide differential and to avoid overcalling a disease state from the gap alone. The anion gap is best used as part of a structured review of the electrolyte panel, the patient’s chemistry history, and any related blood gas or metabolic findings.
- Lactic acidosis: often associated with increased acid production or reduced clearance. Ketoacidosis: linked to ketone accumulation and an elevated gap. Renal failure: associated with retained unmeasured acids. Hypoalbuminemia: may lower the observed gap and hide abnormality.
Factors Affecting Precision in the Laboratory
Accuracy depends largely on sample handling, because lags, contamination, hemolysis, or specimen mix-ups can distort the values used in the calculation. Preserving specimen quality is essential when reviewing any derived measurement. A reliable anion gap begins with dependable source data.
Analytical variation can also impact the result, particularly because the equation depends on several separate measurements. Even minimal variation in sodium, chloride, or bicarbonate can alter the calculated gap. That is why instrument-specific performance and method consistency are important when interpreting an out-of-range result.
The ion-selective electrode method used for electrolyte measurement deserves close attention. Different platforms may show small bias in chloride or sodium measurement, and those differences can affect the final calculation. Laboratory professionals should understand their platform’s behavior and review any https://anion-gap-formula041.cloudhinter.com/posts/anion-gap-calculator-for-medical-students unexpected result in light of the analyzer’s known characteristics.
QC is central to reliable reporting. Routine QC checks, calibrations, and correlation review help reduce the chance that an erroneous measurement will propagate into the calculated gap. When a result seems discordant, confirm that QC is in range, review recent maintenance or reagent changes, and consider whether the value may be affected by analytical drift.
Because the anion gap is a derived value, it is particularly vulnerable to cumulative small errors. Careful review of method, specimen, and control data helps ensure that the output supports accurate clinical support rather than introducing noise into the clinical record.
Best Practices for Documenting and Clinical Communication
Effective lab reporting should display the anion gap in a way that enables immediate clinical correlation. When your laboratory reports the calculated value automatically, ensure that the accompanying note or interpretive comment reflects the local reference range and any assay-specific caveats. Strong communication minimizes the risk that the result is overinterpreted or overlooked.
When the value is critically abnormal or strongly suggestive of a significant acid-base disturbance, use established policies for critical values or urgent notification. Not every abnormal anion gap requires immediate escalation, but results that align with severe metabolic acidosis or a major shift in the chemistry profile may justify prompt communication depending on local policy.
A useful interpretive approach includes comparison with prior results, review of the full panel, and consideration of the delta gap when clinically relevant. The delta gap can help assess whether an additional acid-base process may be present, offering a more nuanced view of complex disorders. This is particularly helpful when the pattern implies more than one disturbance or when the numbers do not fit a simple one-process explanation.
Clear reporting guidance should also note whether the value is corrected for albumin. If the laboratory provides both uncorrected and corrected results, the report should make the distinction obvious so that clinicians can perform accurate result interpretation. Transparent reporting improves trust and encourages more consistent decision-making.
Laboratory professionals add value when they frame the anion gap as a context-based metric rather than a standalone answer. By combining method awareness, analytical review, and thoughtful communication, the laboratory can strengthen the clinical utility of this common chemistry-derived marker.
FAQ About Anion Gap Calculation

What is an anion gap calculator used for in clinical laboratory work?
An anion gap calculator is designed to derive the anion gap from an electrolyte panel and assist with acid-base interpretation. In routine lab work, it helps professionals review patterns consistent with metabolic acidosis, check electrolyte balance, and offer diagnostic support during result review and reporting.
How do you determine the anion gap from sodium, chloride, and bicarbonate?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate, expressed as Na − (Cl + HCO3). Using serum sodium, serum chloride, and serum bicarbonate, the calculation produces the uncorrected anion gap. The value should then be checked against the laboratory’s reference interval.
When should albumin correction be applied to the anion gap?
Albumin correction should be applied when albumin is low, especially in hypoalbuminemia, because reduced albumin can obscure an elevated gap. The albumin-corrected anion gap provides a more accurate corrected value for interpretation when the clinical context suggests that the uncorrected value may be misleading.
What can a high anion gap indicate?
A high result often indicates high anion gap metabolic acidosis, which is a form of metabolic acidosis caused by accumulation of unmeasured acids. Common associations include lactic acidosis, ketoacidosis, and renal failure. As always, the result should be interpreted with clinical correlation and the full chemistry profile.
Can a low anion gap be caused by laboratory error?
Yes. A low anion gap can result from laboratory error, including issues related to specimen handling, analyzer performance, or analytical variation. Before reporting a clinically significant interpretation, laboratory professionals should verify the measurements, review quality control, and consider whether the result is supported by the rest of the serum chemistry data.